A Guide to Clinical Psychedelic Treatment and Medically Supervised Care

Clinical psychedelic care can refer to
several different pathways, each with different oversight, risks, and
expectations.
Contents
1. Introduction and who this guide is for
2. What “clinical” and “medically supervised” mean
3. Major care and access models
4. High-level comparison of principal modalities
5. What the care journey may involve
6. Screening, contraindications, consent, and safety planning
7. How to evaluate a clinic, service center, study, or
program
8. Cost, insurance, travel, legality, and practical access
9. Comparing pathways and deciding what to investigate next
10. Conclusion and next step
1. Introduction and who this guide is for
Interest in psychedelic-related treatment has expanded into several different systems of care. A person researching options today may encounter FDA-approved intranasal esketamine treatment, off-label medical use of racemic ketamine, state-regulated psilocybin or natural-medicine services, clinical trials, and programs outside the United States, including ibogaine programs sought by some U.S. participants. These pathways can look similar in marketing or conversation, but they are not interchangeable. They differ in regulatory status, provider roles, screening and monitoring, evidence, accountability structures, and the legal framework under which the service is delivered. [1]
That distinction is the starting point for this guide. The phrase “psychedelic care” is useful as a broad description, but it does not identify one medical specialty, one treatment model, or one level of oversight. FDA approval for a particular product and labeled use is different from off-label medical use. State-regulated services are different from conventional prescription treatment. Clinical-trial participation is a research pathway, and a registry listing or participation in a study does not establish FDA approval or guarantee therapeutic benefit. Programs outside the United States must be evaluated within the laws and oversight systems of the jurisdiction where they operate; this guide does not infer foreign legality or licensure from a program’s marketing language. [2]
This guide is designed for adults trying to understand those differences before deciding what to investigate further. It explains the major clinical and medically supervised pathways, compares the principal modalities at a high level, describes what screening, consent, supervision, safety planning, and follow-up may involve, and provides a framework for evaluating a provider, service center, study, or program. Where evidence or regulatory requirements are specific to a substance, formulation, protocol, product, or jurisdiction, the guide keeps those limits explicit rather than treating them as universal standards. [3]
The goal is decision support, not a recommendation for any particular psychedelic treatment. Legal or regulatory access does not by itself establish clinical appropriateness, efficacy, or the quality of a particular provider or program. Likewise, promising research does not automatically establish FDA approval, routine-care effectiveness, or equivalence between a research protocol and a commercial or state-regulated service. Readers should evaluate the exact pathway they are considering: what substance or formulation is involved, who provides the service and under what authority, what screening and safety procedures apply, what evidence actually supports the model, and what follow-up or accountability exists. [4]
Research and regulatory information in this article is current through September 1, 2026. Because drug labeling, federal schedules, state rules, licensing systems, clinical trials, and other requirements can change, time-sensitive details should be verified with the relevant regulator, study, or qualified professional before they are relied upon. This guide is educational and does not provide individualized medical or legal advice.
1.1 Why this landscape is unusually easy to misunderstand
Psychedelic care sits at the intersection of medicine, mental-health treatment, controlled-substance law, state experimentation, clinical research, wellness culture, and commercial innovation. Those systems use overlapping language even when their legal and professional structures are different. A reader may see the words “clinic,” “therapy,” “medical,” “licensed,” “research backed,” or “legal” applied to services that operate under very different authorities. [5]
The confusion is not merely semantic. It can affect what a person assumes about screening, emergency readiness, professional accountability, insurance, evidence, and what happens if something goes wrong. Someone may reasonably hear “licensed facilitator” and assume the person is a licensed psychotherapist; hear “ketamine therapy” and assume the drug is FDA approved for depression; or hear “legal psilocybin” and assume federal law has changed. Each inference can be wrong even when the underlying phrase contains a piece of truth. [6]
A useful guide therefore has to do more than list substances. It has to separate the layers that determine what a pathway actually is. Throughout this article, those layers include the substance or product, regulatory status, intended use, provider role, setting, evidence base, screening process, supervision, emergency capability, follow-up, cost, and accountability. When those layers are kept separate, readers can compare unlike systems without pretending they are equivalent.
1.2 What “evidence-based” should mean in this guide
Evidence-based does not mean that every statement comes from the same type of source. Different claims require different authorities. FDA labeling and REMS materials control statements about an approved product and its required use conditions. Statutes and administrative rules control legal and licensing claims within their jurisdictions. Randomized trials can address efficacy under specific research conditions. Systematic reviews can synthesize patterns across studies. Professional guidance can help interpret clinical implementation and ethics. [7]
The source type should match the claim. A randomized trial should not be used as the controlling source for whether a service is currently legal in Oregon. A state website should not be used as proof that psilocybin treats major depressive disorder. A clinic’s marketing page should not be used as independent evidence of its treatment efficacy. This claim-to-source matching is especially important in a field where regulatory change and scientific enthusiasm move quickly.
Evidence strength also varies within the same modality. Esketamine has an FDA-approved product pathway and randomized depression evidence, while racemic ketamine psychiatric care is off-label and protocol-specific. Psilocybin has meaningful randomized evidence in selected research populations but no FDA-approved psilocybin prescription treatment as of this guide’s cutoff. Ibogaine has emerging human observational evidence alongside a serious cardiac-safety literature and federal Schedule I status. [8]
The article therefore avoids flattening “promising,” “supported,” “approved,” and “established” into the same category. Readers deserve to know both what a study found and what remains uncertain.
1.3 Why regulation and quality are related but not identical
Regulation can create important protections: licensure, conduct standards, required disclosures, product controls, recordkeeping, monitoring rules, complaint pathways, and enforcement. But regulation does not guarantee that every provider is equally skilled or that every permitted service has the same evidence base. Conversely, the absence of a particular regulatory category does not by itself prove that every element of a service is poor quality. [9]
This distinction is important because readers can otherwise make opposite mistakes. One is regulatory halo: assuming that because a service is legal or licensed, it must be clinically effective and appropriate. The other is regulatory nihilism: assuming that because a treatment is off-label or investigational, no meaningful evidence or professional standards exist. Both shortcuts obscure the actual questions.
The better approach is to ask what the regulation controls and what it does not. SPRAVATO’s REMS controls specific administration and monitoring requirements. Oregon’s psilocybin rules govern a state service system. Colorado’s natural-medicine rules define facilitator and business requirements. Clinical-trial protections govern research participation. None of these frameworks can simply stand in for the others. [10]
1.4 Who may benefit from using this guide
This guide is most useful before a person has committed to a particular provider or program. It can help someone who has heard about ketamine or esketamine and is unsure how they differ; someone comparing Oregon or Colorado regulated services with conventional mental-health treatment; someone considering a clinical trial; or someone researching an international program and trying to identify what must be independently verified.
It can also help family members, caregivers, clinicians, and support people understand why two programs that both use psychedelic language may require very different due diligence. The framework is intentionally neutral. It does not assume that a medicalized pathway is always preferable, that state-regulated services are equivalent to psychotherapy, or that international programs are inherently unsafe. It asks what can be verified and what evidence applies.
The guide is not designed to tell a reader whether they personally qualify for treatment, whether they should stop a medication, what dose they should receive, or which substance is best for them. Those decisions require individualized professional assessment. It also does not replace deeper modality-specific guides, which can examine the evidence and safety questions for ketamine/esketamine, psilocybin, and ibogaine in substantially more detail.
1.5 How to use the rest of the article
Readers do not necessarily need to read every section in sequence. Someone still trying to understand terminology may start with Section 2. Someone comparing access models may move to Section 3. Readers focused on substances can use Section 4 as a high-level comparison before following deeper modality guides. Sections 5 and 6 explain the care journey and safety framework, while Section 7 provides provider-evaluation questions. Sections 8 and 9 address practical access and comparison.
The recurring discipline is the same throughout: identify the exact pathway, then match claims and expectations to that pathway. When a statement is specific to SPRAVATO, it should not be generalized to ketamine. When a rule is specific to Oregon, it should not be generalized to Colorado. When evidence comes from a selected research population, it should not be presented as proof of universal benefit. When an international program is discussed, its legality and credentials should not be inferred from marketing. [11]
That discipline may make the article feel more cautious than promotional descriptions of psychedelic care. The purpose is not to diminish the field. It is to give readers a map sturdy enough to support real decisions.
2. What “clinical” and “medically supervised” mean
2.1 Why labels can mislead
Words such as “clinical,” “medical,” “therapy,” “treatment,” and “facilitated” can sound reassuring, but the label used by a website or program does not by itself establish what regulatory framework applies, what professional license the provider holds, or how strong the evidence is. The same broad psychedelic-care landscape includes an FDA-approved prescription product, off-label medical use of an approved drug, state-regulated services that are not conventional prescription treatment, and investigational interventions delivered under research protocols. Those categories answer different questions and should not be collapsed into a single idea of “psychedelic treatment.” [12]
For this reason, “clinical” and “medically supervised” are best treated here as practical descriptions that require verification, not as guarantees. A reader still needs to ask: What exactly is being provided? Who regulates it? What license or authorization does the provider hold? Is the substance or formulation FDA approved for this use, used medically outside its labeled indication, delivered through a state-regulated service, or being studied under a research protocol? [12]
 Terms like “clinical”
and “medically supervised” can describe very different environments and levels
of oversight.
2.2 Medical treatment, off-label care, regulated services,
facilitation and research are not synonyms
FDA approval is product- and use-specific. The current SPRAVATO label applies to a particular intranasal esketamine product and specified adult psychiatric indications, with product-specific warnings and REMS-linked requirements. Ketamine injection is separately FDA approved for anesthesia-related indications; psychiatric use of racemic ketamine is outside those labeled indications. Off-label medical use is therefore a different regulatory concept from an unapproved drug or a nonmedical service. Compounded ketamine products are a separate category again: FDA states that compounded drugs are not FDA approved and are not subject to the same premarket review for safety, effectiveness, and quality. [13]
State-regulated psychedelic services create another category. Oregon operates a licensed psilocybin-services model with service centers and facilitators under state law and rules. Colorado operates a distinct natural-medicine system with facilitator licensure and separate regulation of relevant businesses, healing centers, and products. These state systems should not be described as FDA-approved medical treatment merely because they contain screening, consent, supervision, or other health-related safeguards. State authorization also does not change a substance’s separate federal controlled-substance status. [14]
Clinical research is different again. A clinical trial is designed to generate knowledge under a defined research protocol. Eligibility, consent, study procedures, assignment methods, and follow-up are determined by that protocol, and participation does not guarantee therapeutic benefit or assignment to an experimental intervention. A ClinicalTrials.gov listing or promising study result is not the same as FDA approval or established routine treatment. [15]
2.3 Provider license versus program regulation
The professional role of the person delivering a service also matters. A psychedelic-specific facilitator license does not automatically confer medical or psychotherapy scope. In Oregon, current guidance recognizes qualifying dual-license professionals who may conduct preparation and integration under both licenses, while psilocybin-service facilitation and separate healthcare scope remain distinct. Colorado explicitly distinguishes a Facilitator from a Clinical Facilitator and ties clinical diagnosis and treatment authority to the person’s separate qualifying professional license. These distinctions are jurisdiction-specific, but they illustrate a broader due-diligence principle: verify both the psychedelic-service credential and any separate healthcare credential rather than inferring one from the other. [16]
Currentness matters here as well. Oregon enacted additional 2026 amendments affecting parts of the psilocybin framework that are not operative until January 1, 2027; this guide does not treat future-effective provisions as current 2026 authority. Separately, Oregon Psilocybin Services published revised proposed administrative rules for public comment on September 1, 2026. Those proposals are active rulemaking materials, not current operative requirements, and are not treated as effective rules in this guide. [17]
A similar caution applies to the setting. A business calling itself a “clinic” does not establish that every service it offers is FDA approved, that every person providing care is a medical professional, or that the program operates under the same rules as a hospital, physician practice, state service center, or research site. Provider training, certification, licensure, regulatory authorization, and the actual role being performed should be evaluated separately. [18]
2.4 A practical umbrella category without asserting equivalence
This article uses phrases such as “psychedelic-related care” and “clinical or medically supervised pathways” as umbrella language because readers often encounter these options together while researching care. The terminology is organizational, not a claim that the pathways are medically, legally, or scientifically equivalent. Evidence from one compound, formulation, route, diagnosis, protocol, or jurisdiction should not be transferred automatically to another. Randomized efficacy evidence, regulatory authority, and professional ethics guidance also serve different functions; one cannot simply substitute for another. [19]
Throughout the rest of this guide, the more useful question is therefore not simply, “Is this psychedelic care clinical?” It is: What exact pathway is this, what authority governs it, what evidence applies to it, who is authorized to provide which parts of the service, and what protections and limitations come with that model? Keeping those questions separate makes later comparisons of safety, screening, evidence, access, and provider quality substantially more meaningful. [20]
2.5 Regulation operates at several layers at once
One reason psychedelic-related care is difficult to understand is that several regulatory systems can apply simultaneously. Federal drug law addresses controlled-substance status. FDA regulation addresses approval of drug products and conditions of use. State professional-licensing law governs who may practice medicine, psychology, psychotherapy, nursing, or other regulated professions. State psychedelic-service laws can create additional facilitator, service-center, healing-center, product, testing, or operational requirements. Research is governed through a separate framework involving protocols, consent, institutional oversight, and federal requirements. [21]
These layers answer different questions. A substance’s federal schedule does not tell a reader whether a particular state has created a state-authorized service model. A state-authorized service does not tell a reader whether the drug is FDA approved. FDA approval does not tell a reader whether a particular clinician is licensed in good standing. A professional license does not tell a reader whether a provider is authorized to perform every role they advertise. [22]
For consumers, the practical consequence is that verification may require more than one source. A reader evaluating an Oregon psilocybin service, for example, may need to distinguish the service-center license, facilitator license, any separate healthcare credential, current state rules, and the substance’s separate federal status. A reader evaluating esketamine may need to distinguish the product label, REMS requirements, the healthcare setting, and the treating professional’s credentials. [23]
This layered approach prevents a common category error: using one true credential to imply several others. “Licensed” is incomplete unless the license and licensing authority are named. “FDA approved” is incomplete unless the product, indication, and use are clear. “Legal” is incomplete unless the jurisdiction and activity are specified. “Clinical” is incomplete unless the actual care relationship and professional role are identified.
2.6 Medical oversight is a function, not a marketing adjective
The phrase “medical oversight” can refer to very different arrangements. In one program, a physician may directly evaluate the patient, prescribe the intervention, remain responsible for treatment, and supervise monitoring. In another, a medical professional may review records or be available for consultation while facilitators deliver the core service. In research, a study physician may hold protocol-specific safety responsibilities. In an international program, the title may be used without enough information for a U.S. reader to understand the local credential or scope. [11]
The meaningful questions are therefore functional. Who takes the medical history? Who reviews medications? Who decides whether further evaluation is needed? Who is responsible during administration? What physiologic monitoring occurs? Who can diagnose and treat an acute complication? Who determines whether discharge is appropriate? Who manages problems after the participant leaves? [24]
A program does not need the same answer to every question as another pathway. SPRAVATO has product-specific requirements that should not be generalized. State-regulated services have their own defined roles. The point is transparency: “medically supervised” should resolve into identifiable people, credentials, responsibilities, and capabilities. [25]
2.7 “Psychedelic-assisted therapy” can refer to a package rather
than a single intervention
The phrase “psychedelic-assisted therapy” often combines several elements: a psychoactive drug, preparation, interpersonal support during the acute experience, psychotherapy or another structured psychological intervention, and post-session integration. Research programs vary considerably in how these elements are designed. Some trials explicitly study a treatment package; others focus more narrowly on a drug intervention delivered with standardized support. [26]
That variation matters when interpreting evidence. If both study groups receive substantial psychological support, the trial may estimate the added effect of the drug within that support structure rather than the effect of the entire package versus no treatment. If a waiting-list design compares immediate treatment with delayed treatment, therapist contact, expectancy, and the broader treatment experience may differ between groups. These are not reasons to discard the results; they are reasons to describe what the design can and cannot isolate. [27]
The same caution applies when a commercial program adopts the language of a research protocol. A program should not imply that it reproduces a published treatment simply because it uses the same substance or offers preparation and integration. Training, participant selection, protocol fidelity, monitoring, therapeutic framework, and follow-up can differ substantially. [28]
2.8 “Integration” is a broad family of practices
Integration has become one of the most widely used terms in psychedelic care, but the literature describes diverse approaches rather than a single standardized intervention. Integration may involve reflection on the experience, meaning-making, behavioral planning, psychotherapy, peer support, spiritual or existential discussion, or other forms of post-session support. [29]
Because of that diversity, the presence of “integration” on a program website tells a reader relatively little by itself. Useful follow-up questions include who provides it, what training and professional scope that person has, what the sessions are intended to do, whether the service is psychotherapy, how many contacts are included, and what happens if clinically significant symptoms emerge. [30]
The distinction is especially important when providers imply that integration is scientifically proven to be the mechanism that makes psychedelic treatment effective. The audited evidence does not establish one universal integration model as independently necessary or sufficient for clinical benefit. Integration may still be valuable to participants, but its role should be described proportionately to the evidence. [31]
2.9 Credentials should be read as a stack, not a single badge
A provider may hold several different forms of credentialing at once: a state healthcare license, a psychedelic facilitator license, a private training certificate, continuing-education credentials, research experience, or institutional privileges. Each credential answers a different question. [32]
A state professional license can establish legal authority within a defined healthcare scope, but it does not necessarily demonstrate specialized psychedelic training. A private psychedelic certificate may demonstrate completion of a curriculum, but it does not independently authorize medical practice or psychotherapy. A facilitator license may authorize activities within a state psychedelic-service framework without creating prescribing authority. Research experience may demonstrate familiarity with protocols without establishing that a commercial service reproduces the evidence base. [33]
For readers, this means provider evaluation should move beyond asking whether someone is “certified.” The better question is certified or licensed as what, by whom, for which role, in which jurisdiction, and with what accountability mechanism? The answer should correspond to the service the provider is actually offering.
3. Major care and access models
 Psychedelic-related
care is not one pathway but several distinct systems of access and oversight.
The practical differences among psychedelic-related pathways become clearer when they are compared by regulatory status, substance or formulation, provider role, screening and monitoring, evidence, and accountability. No single pathway described below should be treated as the default model for all psychedelic care. [5]
3.1 FDA-regulated esketamine treatment
Intranasal esketamine (SPRAVATO) is the clearest example in this guide of an FDA-approved psychedelic-adjacent psychiatric drug pathway. Its approval is product-, route-, and indication-specific, and the current label governs the authorized uses. SPRAVATO remains subject to an FDA-required REMS; outpatient administration occurs in certified healthcare settings under direct observation, with product-specific monitoring that includes at least two hours of post-administration observation. [34]
That regulatory status matters because esketamine should not be used as shorthand for ketamine generally. Randomized evidence supports short-term antidepressant benefit in selected treatment-resistant-depression populations, and a responder-enriched randomized-withdrawal study found lower relapse risk when prior responders or remitters continued esketamine plus an oral antidepressant rather than discontinuing esketamine. Those maintenance findings do not establish that every patient who starts esketamine will benefit or that one maintenance schedule is universally optimal. Acute treatment can also involve dissociation, dizziness, blood-pressure increases, sedation, and other tolerability effects. [35]
For a reader evaluating this pathway, the central questions are relatively concrete: Is the treatment the FDA-approved intranasal esketamine product? What current indication is being treated? Is administration occurring under the applicable REMS and monitoring requirements? What does the provider’s screening, medication review, observation, discharge, and follow-up process involve? [34]
3.2 Off-label racemic ketamine care
Racemic ketamine occupies a different regulatory category. FDA-approved ketamine injection exists for anesthesia-related indications, while psychiatric use of racemic ketamine is outside those labeled indications. Compounded ketamine products are a separate category and are not FDA approved; FDA does not review compounded drugs for safety, effectiveness, or quality before marketing in the same way it reviews approved products. [36]
The evidence is protocol-specific. Evidence-graded guidance and controlled studies support short-term antidepressant effects for monitored intravenous racemic ketamine in selected treatment-resistant-depression populations. Repeated and maintenance findings remain more limited and heterogeneous; small studies do not establish one universal number of infusions, one maintenance frequency, or one route that should be treated as the standard ketamine protocol. [37]
Because real-world ketamine services can differ substantially, readers should identify the formulation and route being offered, the prescriber’s credentials, the indication being treated, the screening and monitoring process, and what happens if a medical or psychiatric problem develops during or after treatment. A clinic’s use of ketamine does not by itself establish that its protocol matches the strongest available research or the monitoring used in a particular trial. [38]
3.3 Oregon regulated psilocybin services
Oregon provides a distinct state-regulated access model. Under Oregon law, adults age 21 and older may receive psilocybin services within the licensed system; clients purchase, possess, and consume regulated psilocybin products at licensed service centers under the supervision of licensed facilitators. The framework includes preparation, administration, and integration-related processes, but it is a state-licensed service model rather than FDA-approved prescription treatment. Psilocybin remains federally listed in Schedule I as of the September 1, 2026 cutoff, so Oregon authorization should not be described as changing federal scheduling. [39]
Provider scope is especially important in this model. An Oregon psilocybin facilitator license does not by itself establish that the facilitator is a physician, psychologist, or psychotherapist. Current Oregon guidance recognizes specified dual-licensure arrangements for qualifying professionals, but psychedelic-service licensure and separate healthcare licensure remain distinct. Consumers should verify current license status and applicable scope through official state resources rather than relying only on provider marketing. [40]
Oregon’s framework also illustrates why state-program requirements must not be converted into universal medical contraindications. Current rules and implementation materials contain Oregon-specific intake, consent, preparation, safety, transportation, records, and reporting requirements. Those requirements apply within Oregon’s regulated system and should not be presented as national standards for psychedelic care. [41]
3.4 Colorado regulated natural-medicine services
Colorado has developed its own regulated natural-medicine framework rather than simply copying Oregon’s system. It includes facilitator licensure and separate regulation affecting healing centers, businesses, products, administration, testing, tracking, and other operational requirements. Colorado’s professional rules distinguish a Facilitator from a Clinical Facilitator; the latter must also hold a qualifying Colorado clinical license, and clinical diagnosis or treatment remains tied to that separate professional scope. [42]
For consumers, the important point is that Colorado should be evaluated on its own current rules. Screening, informed consent, administration-session procedures, safety processes, touch and boundaries, recordkeeping, and professional scope may be regulated within the Colorado framework, but those requirements should not automatically be transferred to Oregon, research studies, ketamine clinics, or programs elsewhere. [43]
Colorado’s 2026 ibogaine legislation requires an additional distinction. The enacted law creates a conditional ibogaine research-pilot pathway with funding and federal-approval contingencies; it does not establish routine, generally available ibogaine treatment in Colorado. State authorization, federal drug regulation, professional licensure, and clinical evidence remain separate questions. [44]
3.5 Clinical trials and investigational access
Clinical trials provide another possible access route, but they are research rather than a guarantee of treatment. A study protocol determines who may participate, what intervention is administered, how safety is monitored, what comparison or control may be used, and how outcomes are measured. Informed consent is voluntary and ongoing, and participation should not be presented as guaranteeing enrollment, assignment to an active intervention, or direct therapeutic benefit. [45]
Registered psychedelic studies can help readers identify areas of active investigation, but registry status is not evidence that an intervention has been FDA approved or proven effective. Trial eligibility criteria are also study-specific. Exclusion of a medication, diagnosis, or medical condition from one protocol does not automatically establish a universal contraindication outside that study. [46]
For readers considering research participation, useful questions include what phase and purpose the study has, what is known and unknown about the intervention, what procedures and follow-up are required, what alternatives exist, what costs or compensation apply, and whom to contact about concerns or withdrawal. [45]
3.6 Programs outside the United States
Some U.S. participants travel internationally for psychedelic-related programs, including interventions that are unavailable through ordinary U.S. clinical pathways. The audited ibogaine evidence includes one prospective observational cohort of U.S. Special Operations Forces veterans who independently sought magnesium–ibogaine treatment abroad. That study documents cross-border treatment-seeking, but it does not establish the legality, licensing system, consumer protections, or quality of the country or facility involved. [47]
Accordingly, this guide does not characterize a foreign facility or program as licensed, legal, clinically validated, or medically equivalent to a U.S. pathway without current jurisdiction-specific controlling evidence. A program’s location outside the United States also does not change ibogaine’s separate U.S. federal Schedule I status. Cross-border care should therefore be evaluated by identifying the exact country and local framework, the provider and facility credentials that can actually be verified, the level of medical supervision and emergency readiness, and what recourse exists if something goes wrong. [48]
This caution is especially important for ibogaine. Human benefit evidence remains emerging: the audited 30-person veteran cohort reported substantial post-treatment improvements, but the uncontrolled observational design cannot establish that ibogaine caused those changes or validate the program where treatment occurred. By contrast, the cardiac safety concern is well supported: current review evidence identifies QT prolongation and potentially life-threatening ventricular arrhythmias, with mechanistic and human case evidence providing corroboration. These sources do not provide a reliable population-wide incidence or show that screening can eliminate the risk. [49]
3.7 Comparing the pathways without ranking them
These pathways can be compared meaningfully without declaring one universally superior. The relevant dimensions are regulatory status; the exact substance, formulation, and route; indication or eligibility; provider credentials and scope; setting; screening and consent; monitoring and emergency planning; psychological support; follow-up; accountability; and the strength and limits of the applicable evidence. [50]
Those distinctions also prevent a common reasoning error: evidence or safeguards from one model cannot simply be borrowed to validate another. FDA approval of SPRAVATO does not validate every ketamine protocol. Positive psilocybin trials do not establish the effectiveness of every state-regulated or international program. A state license does not prove clinical superiority. A clinical-trial listing does not equal approval. And a medically styled setting does not substitute for verifying who is providing care, under what authority, with what evidence and safety system. [51]
3.8 Approved medical treatment is not the same as a
standardized psychedelic-care model
Even within conventional healthcare, the phrase “medical treatment” can hide meaningful variation. FDA approval establishes that a specific product is approved for specified uses under its labeling; it does not create one universal model for every clinic that administers the product. Clinics can differ in intake processes, scheduling, coordination with existing care, patient education, follow-up, and how they manage issues that fall outside the minimum product requirements. [34]
For SPRAVATO, the label and REMS provide unusually concrete anchors. They define product-specific requirements and warnings that can be checked against current official materials. That makes it possible for a reader to distinguish mandatory elements from optional clinic practices. A clinic may add psychotherapy, additional preparation, or other supportive services, but those additions should be described as additions rather than implied to be FDA-required components of the approved product. [52]
The same logic applies to claims about outcomes. FDA approval does not mean every patient will respond, and a clinic’s own success rate should not be assumed to equal results from pivotal trials unless the population, outcome definition, follow-up, and analysis are genuinely comparable. Readers should be cautious when regulatory status is used rhetorically to imply certainty beyond what the label and evidence establish. [53]
3.9 Off-label medicine still requires intervention-specific reasoning
Off-label prescribing is sometimes described either as inherently experimental or as automatically established medical practice. Neither shortcut is adequate. Off-label use refers to use of an approved drug outside the approved labeling; the strength of evidence for a particular off-label use can range widely. For psychiatric ketamine, controlled evidence and professional guidance support specific monitored uses, particularly IV racemic ketamine in selected depression populations, while important questions remain about route, repeated treatment, maintenance, and longer-term management. [54]
This makes formulation and route essential. Evidence from IV ketamine cannot simply be assigned to every oral, sublingual, intramuscular, intranasal compounded, or at-home model. FDA’s compounded-ketamine warning reinforces the regulatory distinction: compounded products are not FDA approved and have not undergone the same premarket review as approved products. [55]
A responsible off-label program should therefore be able to explain why its particular protocol is being used, what evidence is most directly relevant, what is extrapolated, and what remains uncertain. The existence of medical licensure is necessary for medical prescribing but does not by itself resolve the evidence question. [56]
3.10 State-regulated access creates consumer protections
without converting the service into FDA-approved treatment
Oregon and Colorado demonstrate that a state can create structured legal access with licensing, conduct rules, screening processes, product controls, records, and other safeguards even when the underlying substance is not FDA approved as a prescription treatment. That distinction is central to understanding the contemporary U.S. landscape. [57]
These systems can provide meaningful consumer-protection mechanisms. A participant can verify licenses, identify a regulator, review rules governing conduct, and understand required parts of the service process. At the same time, state regulation does not answer every medical question. It does not automatically establish efficacy for a diagnosis, convert facilitators into healthcare professionals, or make the state service equivalent to a clinical trial. [58]
The distinction also protects state programs from being judged by the wrong standard. A regulated adult-service system may have goals and eligibility structures that differ from psychiatric treatment. Describing it accurately is more useful than either medicalizing it beyond its legal scope or dismissing it because it does not resemble conventional healthcare. [59]
3.11 Research access involves protections and burdens that
routine care may not share
Clinical research can offer access to interventions that are not otherwise available, but participation also serves the scientific aims of the study. Participants may undergo additional assessments, questionnaires, laboratory procedures, imaging, randomization, or follow-up that exist because of the research question rather than because they would be required in ordinary care. [15]
Research protections such as informed consent, protocol oversight, adverse-event reporting, and defined eligibility are important, but they should not be translated into a claim that research participation is inherently safer or better than every form of clinical care. A study may investigate an intervention precisely because important questions remain unanswered. The ethical framework is designed to manage that uncertainty, not erase it. [60]
Potential participants should also understand therapeutic misconception: the understandable tendency to interpret research primarily as individualized treatment. A trial team may provide careful clinical attention, yet protocol requirements and scientific design still govern participation. Asking about randomization, alternatives, withdrawal, post-trial care, costs, compensation, and whom to contact with concerns helps preserve the distinction. [45]
3.12 Cross-border care magnifies verification problems
International psychedelic programs are often discussed as a single category, but they span different countries, substances, legal systems, professional standards, and facility types. The audited evidence for this article does not support a broad claim that international psychedelic care is either generally safe or generally unsafe, legal or illegal, medical or nonmedical. Those determinations require jurisdiction- and program-specific evidence. [47]
What can be said more confidently is that distance makes verification more important. A U.S. participant may be unfamiliar with the local licensing system, emergency infrastructure, complaint process, language, record practices, or standards for professional titles. A facility may use terms such as “medical,” “clinical,” or “hospital-grade” in marketing, but those terms should be corroborated against the actual authority governing the site and staff. [61]
Cross-border programs also create continuity questions. If an adverse event or psychiatric concern develops after the participant returns home, what information is available to the person’s usual clinicians? If emergency transfer is required during the program, where does the participant go? If a dispute or injury occurs, what recourse exists? These questions become especially important for interventions such as ibogaine, where the audited evidence identifies a serious cardiac-risk domain. [49]
3.13 A pathway can be responsible without looking like another
pathway
The purpose of comparing care models is not to force convergence. A research site should not be expected to operate like a commercial psychiatric practice; a state service center should not be mislabeled as a clinical trial; and an off-label ketamine clinic should not imply that its treatment inherits SPRAVATO’s approval. Each pathway should instead be evaluated for internal coherence. [62]
Internal coherence means that the legal authority, provider role, evidence claims, screening, consent, monitoring, emergency plan, records, and follow-up all fit the service actually being offered. When those elements align, readers can make a more informed comparison. When they conflict—for example, when a nonmedical program makes disease-treatment claims, a clinic blurs compounded ketamine with FDA-approved esketamine, or a provider uses research findings to imply guaranteed results—the mismatch itself is a reason for closer scrutiny. [63]
3.14 Provider role can change within the same organization
A single organization may offer more than one kind of service. A medical practice might provide medication management, psychotherapy, and ketamine administration. A state-regulated service center may host facilitators who also hold separate professional licenses. A research institution may operate clinical services outside the study. The organization’s identity therefore does not automatically determine the legal or professional status of every encounter. [64]
Readers should ask which role the provider is performing in the specific service under consideration. A psychologist who is also an Oregon facilitator may have one set of responsibilities when practicing psychotherapy and another when acting within the psilocybin-services framework. Colorado’s distinction between Facilitator and Clinical Facilitator similarly shows why role and scope must be tied to the actual service. [65]
This prevents credential spillover: the tendency to assume that because a provider possesses a respected license, every service they offer falls under that license or receives the same regulatory protections.
3.15 Product regulation and professional regulation solve different
problems
Drug regulation asks questions about products, indications, manufacturing, labeling, and conditions of use. Professional regulation asks who may practice within a defined scope and how that professional is accountable. Service regulation can add rules about facilities, conduct, products, records, or operations. [66]
SPRAVATO demonstrates product-specific regulation through labeling and REMS. Oregon and Colorado demonstrate service and facilitator regulation. A medical license governs professional practice but does not transform an unapproved product into an approved one. A state service-center license can authorize activities under state law but does not create federal approval. [67]
When consumers ask whether something is “regulated,” they should therefore ask what is regulated: the drug, the professional, the facility, the service process, the research protocol, or some combination.
3.16 Legal access can exist without a disease-treatment claim
State-regulated adult services can be misunderstood when readers assume that legal access must be justified through a medical diagnosis. Oregon’s psilocybin framework and Colorado’s natural-medicine system are distinct from conventional FDA prescription pathways. [58]
That distinction matters because medicalizing every state service can distort both provider scope and consumer expectations. A facilitator may support a regulated service without diagnosing or treating a psychiatric disorder unless they separately hold and are acting within a qualifying clinical license. [68]
Conversely, the absence of a required diagnosis does not mean that participants cannot have health-related goals. It means the legal structure of the service should be described accurately rather than retrofitted into conventional medical terminology.
3.17 Research and routine care use evidence differently
Research generates evidence under a protocol. Routine care uses existing evidence, professional judgment, product labeling, and clinical standards to make individualized decisions. These functions overlap but are not identical. [60]
A research protocol may restrict medications, diagnoses, ages, or medical conditions to protect participants or reduce confounding. A clinician may face a different question: whether a particular treatment is appropriate for an individual patient under medical practice. A state facilitator may face yet another question defined by service rules and scope. [69]
This is why the claim map for this article treats trial exclusions as protocol facts rather than universal contraindications. It is also why publication should resist language such as “people with X can never receive psychedelic treatment” unless controlling evidence actually supports that breadth.
3.18 Cross-border programs should be evaluated country by
country
The category “international psychedelic treatment” is too broad to support legal or regulatory conclusions. Countries differ in drug law, medical licensure, facility regulation, emergency infrastructure, and consumer remedies. Even within one country, different substances or service models may fall under different rules. [47]
A responsible directory or educational guide should therefore avoid statements such as “ibogaine is legal abroad” or “international clinics are medically regulated” without naming the jurisdiction and current authority. The fact that a published cohort received treatment outside the United States does not answer those questions. [47]
Program-specific due diligence may require checking the facility, individual clinicians, local licenses, emergency arrangements, and applicable drug law separately. This is a deeper research task than the gateway article can complete for every destination.
3.19 Marketing categories are not regulatory categories
Terms such as “psychedelic clinic,” “healing center,” “retreat,” “treatment center,” “wellness program,” and “therapy center” may be used differently across jurisdictions. Some are legally defined in particular systems; others are ordinary marketing language. [59]
Readers should therefore avoid assuming that two organizations using the same label operate under the same rules. “Healing center” has specific relevance in Colorado’s framework, while a business elsewhere using the same phrase may not be part of that system. “Clinic” can describe a medical practice but can also be used informally. [43]
The underlying verification questions remain more reliable than the label: what authority governs the organization, who provides the service, what product or substance is involved, and what accountability exists?
3.20 Consumer protection is broader than medical monitoring
Safety discussions often focus on physiologic monitoring, but consumer protection also includes truthful advertising, transparent fees, informed consent, boundaries, records, privacy, complaint mechanisms, and the ability to verify credentials. [70]
A service can have strong medical monitoring and still create problems if it misrepresents evidence or uses coercive boundaries. Conversely, a well-intentioned facilitator can provide strong interpersonal support while lacking the medical capability needed for a higher-risk intervention. Responsible evaluation considers the whole system.
Oregon and Colorado provide examples of formal service rules that extend beyond the administration session. Research protections likewise include consent and oversight beyond immediate medical monitoring. [71]
3.21 The strongest pathway is the one accurately described and
appropriately matched
This guide intentionally avoids naming a universally “best” model. Different people may prioritize different combinations of evidence, medical oversight, legal access, setting, cost, and follow-up. The article’s task is to make those tradeoffs visible without converting them into individualized treatment advice.
A pathway becomes easier to evaluate when its claims are accurate, its authority is clear, its evidence is proportionate, its screening and monitoring fit the intervention, its boundaries are defined, and its follow-up responsibilities are understandable. [72]
That standard applies whether the pathway is highly medicalized, state regulated, investigational, or cross-border. Accuracy and coherence are the common denominator.
4. High-level comparison of principal modalities
Comparing psychedelic-related modalities requires more than asking which substance has produced positive study results. The relevant evidence differs in maturity, regulatory status, formulation, route, diagnosis, treatment structure, and safety profile. A positive finding for one protocol should not be transferred automatically to another formulation, another condition, or a commercial service that uses the same substance name. [73]
4.1 Ketamine and esketamine
Ketamine and esketamine are related, but they are not interchangeable treatment categories. SPRAVATO is an FDA-approved intranasal esketamine product with psychiatric indications defined by its current label and a continuing REMS framework. Ketamine injection is separately FDA approved for anesthesia-related indications, while psychiatric use of racemic ketamine is outside those labeled indications. Compounded ketamine is a separate category again: compounded products are not FDA approved and do not undergo the same FDA premarket review as approved drugs. [13]
For esketamine, randomized evidence is comparatively developed. A phase 3 trial found that, in selected adults with treatment-resistant depression, supervised intranasal esketamine combined with a newly initiated oral antidepressant produced greater improvement in depressive symptoms at day 28 than oral antidepressant plus placebo nasal spray. A separate randomized-withdrawal maintenance trial found that, among patients who had already achieved stable response or remission on esketamine plus an oral antidepressant, continuing esketamine delayed relapse compared with switching the nasal spray to placebo while continuing the antidepressant. [74]
Those maintenance findings need an important qualification. Randomized-withdrawal designs enroll people who have already tolerated and benefited from treatment before the maintenance comparison, so they do not estimate maintenance benefit for every patient who begins esketamine. Historical trials also should not be used to override current FDA labeling; the current label, not an older trial requirement, controls the approved-use description. [75]
Racemic ketamine has controlled evidence for rapid or short-term antidepressant effects in particular monitored intravenous protocols for treatment-resistant depression. In one small randomized trial, a single IV ketamine infusion produced greater short-term improvement than midazolam; repeated open-label infusions were associated with additional improvement, and prior responders maintained improvement during a short four-week weekly-continuation phase. Those repeated and maintenance phases were not controlled, so they do not establish an optimal number of infusions or a universal maintenance schedule. [76]
Maintenance racemic-ketamine evidence remains less standardized. Professional guidance and implementation reviews emphasize uncertainty around repeated-treatment strategy, durability, route, and longer-term management. A commercial protocol offering a fixed series or indefinite maintenance plan therefore should not be described as “the evidence-based ketamine protocol” without protocol-specific support. [56]
Safety and tolerability also overlap without being identical. Randomized depression-trial evidence reports short-term effects such as dizziness, dissociation, nausea, sedation, blood-pressure increases, and other psychiatric or neurologic effects. A 2025 meta-analysis suggested a possible short-term tolerability advantage for esketamine, but the comparison was largely indirect; direct head-to-head evidence was insufficient to establish that esketamine is definitively safer than racemic ketamine. For SPRAVATO, current FDA labeling and REMS requirements remain the controlling sources for approved-product warnings, monitoring, and administration requirements. [77]
The practical takeaway is not that one form is universally preferable. It is that readers should identify exactly what is being offered—FDA-approved intranasal esketamine, ketamine used medically outside its labeled psychiatric indications, a compounded formulation, or another product—and then evaluate the evidence, route, indication, supervision, monitoring, and follow-up that actually apply to that category. [78]
4.2 Psilocybin-related care

Psilocybin presents a different evidence-and-access picture. It remains federally listed in Schedule I as of the September 1, 2026 cutoff, while Oregon and Colorado have created state-regulated pathways with their own rules. Those state systems should not be confused with FDA approval or with the exact psychological-support structures used in depression trials. [79]
Within clinical research, several randomized depression studies provide meaningful but nonuniform evidence. In a 2023 randomized trial of selected adults with major depressive disorder, a single 25-mg psilocybin dose delivered with protocolized psychological support produced greater reductions in depressive symptoms and functional disability through the studied six-week follow-up than niacin active placebo delivered with the same support structure. The design does not establish the independent contribution of the support component, and the selected research population limits automatic generalization to routine care. [80]
A smaller randomized immediate-versus-delayed-treatment trial also reported rapid, large short-term reductions in depression severity after two psilocybin sessions delivered within a supportive-psychotherapy package. But the waiting-list design did not control for therapist contact, preparation, expectancy, or the acute psychoactive experience and therefore cannot isolate psilocybin from the broader treatment package. [81] This is an example of why positive findings should be described together with the design features that limit causal interpretation.
Direct comparison with an established antidepressant also produced a more qualified result. In a small six-week trial comparing a psilocybin-based treatment package with an escitalopram-based treatment package, the prespecified primary depression outcome did not show a statistically significant between-group difference. Several secondary outcomes favored psilocybin, but those analyses were not corrected for multiple comparisons. The study therefore does not establish that psilocybin is superior to escitalopram or to SSRIs generally. [82]
Interpretation is further complicated by expectancy and blinding. Psychedelic effects can make treatment assignment easier to guess, potentially influencing participants, clinicians, or raters. Methodological reviews and systematic risk-of-bias work identify functional unblinding, expectancy, incomplete masking assessment, and selected samples as recurring interpretive concerns in the psychedelic trial literature. These limitations do not mean positive findings are merely placebo; they mean effect estimates should be interpreted with awareness that expectancy, context, and drug effects may interact and that the magnitude of masking-related bias remains uncertain. [83]
The acute safety picture is better characterized than rare or long-term risk. A systematic review and meta-analysis of randomized therapeutic-dose trials found higher acute risks of headache, nausea, anxiety, dizziness, and elevated blood pressure with psilocybin than with comparators. Broader safety reviews indicate that serious and medically significant events were uncommon but did occur in monitored clinical and research settings, while inconsistent adverse-event ascertainment limits confidence in precise incidence estimates and longer-term risk. [84]
Psilocybin research also commonly includes preparation, supported dosing, and post-session integration, but those components are heterogeneous. The literature does not establish one universally validated psychedelic psychotherapy protocol or prove that a particular integration method independently causes better outcomes. [31] Those research structures should not be silently equated with state-regulated facilitation.
4.3 Ibogaine programs
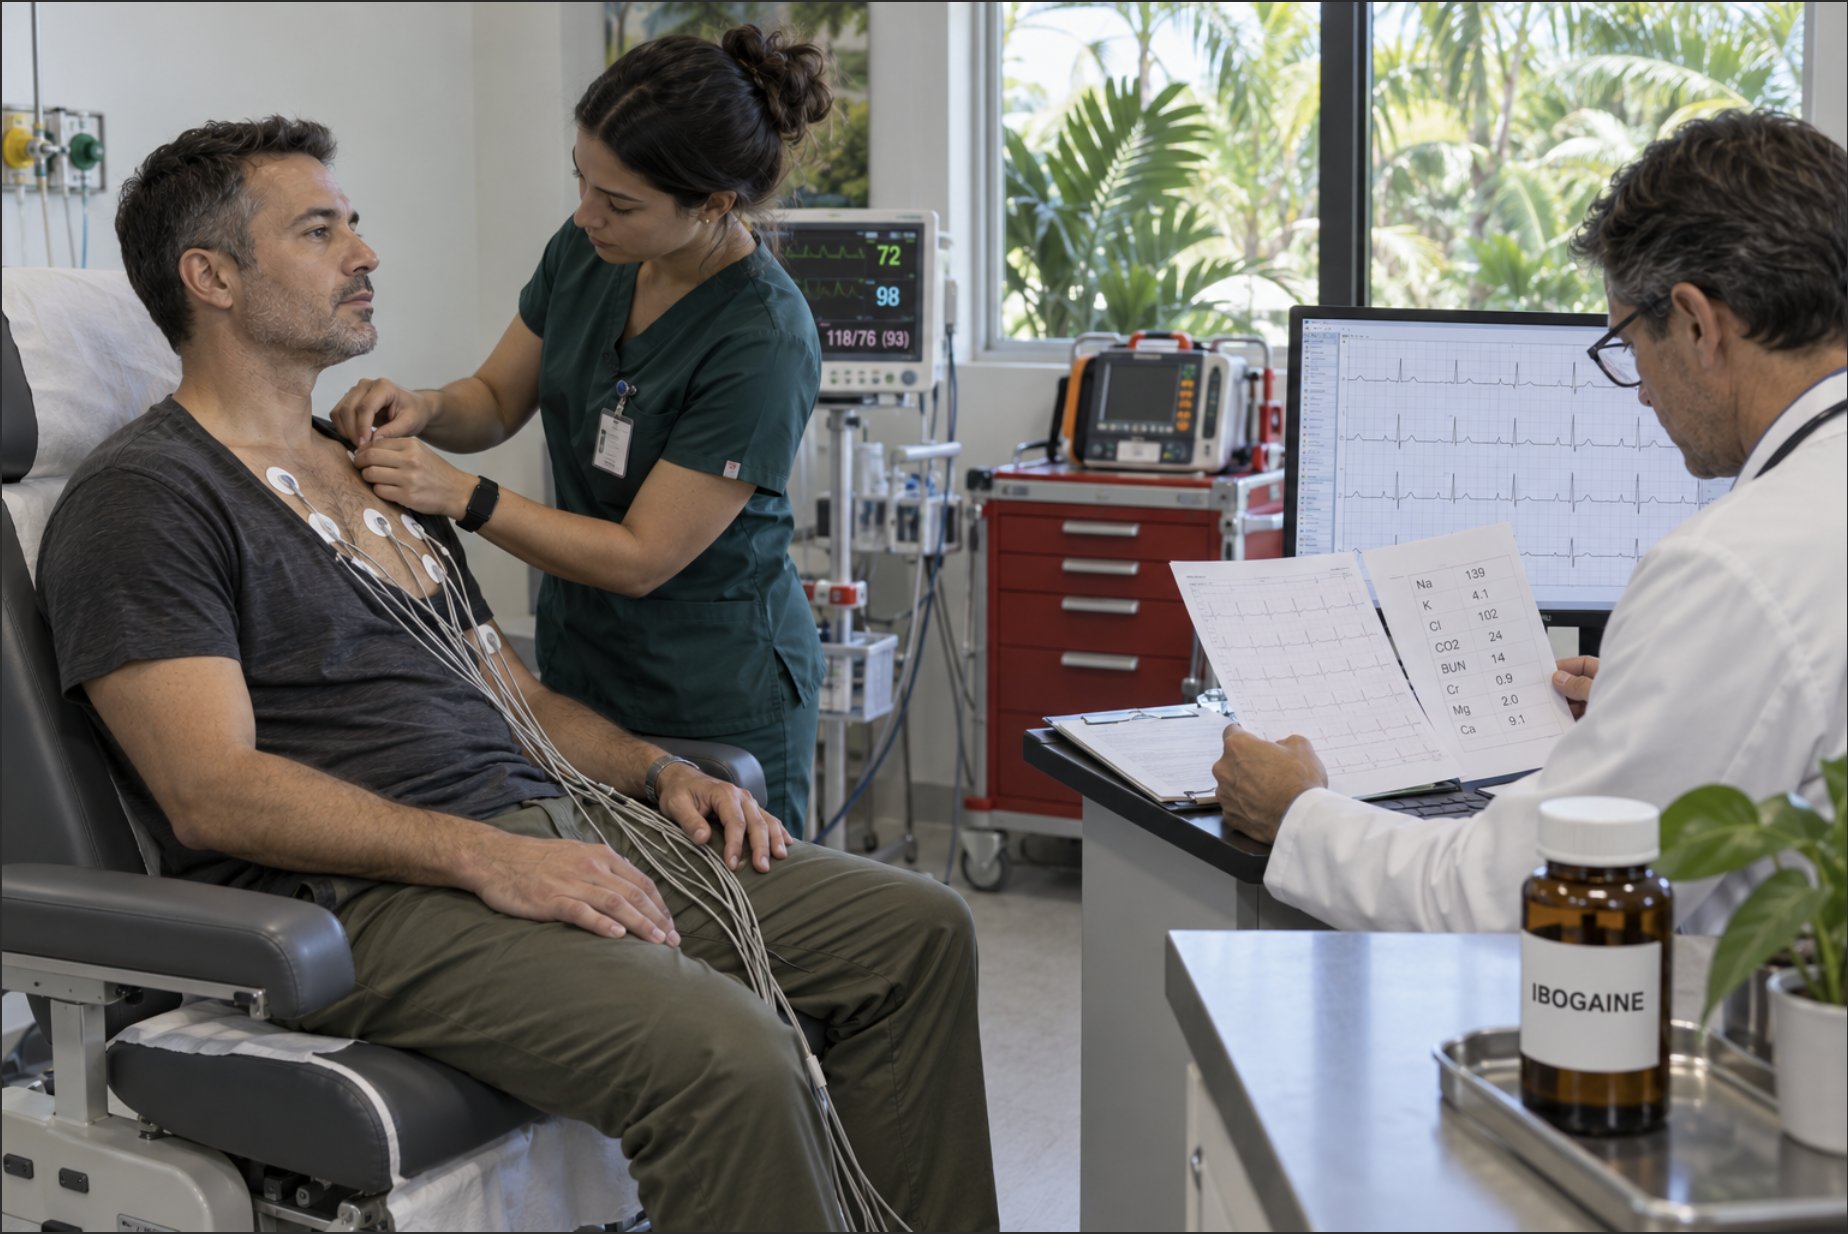
Ibogaine requires a substantially more cautious evidence frame. It is federally listed in Schedule I as of the September 1, 2026 cutoff, and the audited human benefit evidence in this article is observational rather than confirmatory. A prospective study of 30 Special Operations Forces veterans who independently sought magnesium–ibogaine treatment outside the United States reported improvements in disability and psychiatric symptom measures after treatment. However, there was no randomized or untreated control group, so the design cannot determine how much change resulted from ibogaine itself rather than expectancy, setting, selection, co-interventions, regression to the mean, or other factors. [48]
That makes the current benefit evidence hypothesis-generating rather than confirmatory. The study can support saying that substantial improvements were reported in a selected observational cohort and that further research is warranted. It cannot establish ibogaine as an effective treatment for TBI, PTSD, depression, addiction, or other conditions, and it cannot validate the quality, legality, or safety of the facility where participants received care. [47]
The cardiac safety signal is much firmer and deserves disproportionate attention. A 2026 clinical review synthesized evidence that ibogaine and its metabolite noribogaine can prolong cardiac repolarization and QTc and can precipitate ventricular tachyarrhythmias, including torsades de pointes. Mechanistic human-cell research supports biological plausibility for delayed repolarization, while a human toxicokinetic case report documents severe, prolonged multiple arrhythmias after a specific ibogaine exposure. [85]
These sources do not provide a reliable population-wide incidence of serious cardiac events, nor do they show that a particular screening protocol can eliminate the risk. They do establish why cardiovascular assessment, medication/substance review, monitoring, and emergency capability are central questions when evaluating an ibogaine program. [85] A program’s claim that it screens participants should therefore not be treated as proof that ibogaine has been made risk-free.
International access adds another layer of uncertainty. The observational veteran study demonstrates that U.S. participants may seek ibogaine treatment abroad, but it does not establish the legality, licensing system, consumer protections, or quality of any country or facility. [47] This gateway guide therefore does not rank international programs or generalize about their regulation. Verification has to be jurisdiction-specific.
The evidence hierarchy is important here. Ketamine/esketamine and psilocybin have randomized psychiatric evidence bases that allow more direct discussion of efficacy within specific protocols. The audited ibogaine benefit evidence used in this article is observational and uncontrolled, while the cardiac-risk evidence is strong enough to require prominent qualification. Presenting these modalities with equal evidentiary confidence would misrepresent the source record. [86]
4.4 Clinical trials and emerging treatments
Clinical research is where many psychedelic-related interventions remain. A trial may investigate a new compound, a new indication, a psychological-support combination, a dosing structure, or a way to improve safety and durability. But research participation has a different purpose from ordinary clinical care: the protocol is designed to answer a scientific question, and the participant may encounter eligibility restrictions, randomization, placebo or active comparators, additional assessments, and follow-up requirements that would not necessarily exist in routine care. [60]
Informed consent is an ongoing process, participation is voluntary, and participants may withdraw. At the same time, consent should not be mistaken for a promise of therapeutic benefit. Enrollment itself may not be guaranteed, and a randomized study may not assign every participant to the experimental intervention. [45]
ClinicalTrials.gov records are useful for confirming study status, sponsor, design, eligibility, locations, and protocol identifiers. They are not independent proof that an intervention works, and the registry itself should not be treated as government approval of a study’s safety or science. The audited COMP001 registry record is therefore used here for study identity and protocol metadata, not as independent efficacy evidence. Likewise, exclusions listed in a research protocol are study eligibility criteria, not automatically universal medical contraindications. [87]
The appropriate question when reading about an “emerging treatment” is therefore not simply whether a trial exists. It is what phase and design the study has, whether outcomes have been published in an auditable source, how strong the comparator is, how long participants were followed, what safety information was collected, and whether later independent research has corroborated the result. [88]
4.5 Concise modality comparison
A useful comparison should show differences without turning them into a winner-and-loser ranking:
· Esketamine: FDA-approved intranasal product for specific adult psychiatric indications under
current labeling and REMS requirements; randomized short-term and responder-enriched relapse-prevention evidence; supervised administration and acute dissociation, blood-pressure, sedation, and tolerability considerations are central. [89]
· Racemic ketamine: FDA-approved ketamine injection is labeled for anesthesia-related
indications, while psychiatric use is outside those labeled indications; monitored IV evidence supports short-term antidepressant effects in selected TRD populations, while repeated and maintenance strategies remain heterogeneous; compounded products require separate regulatory evaluation because they are not FDA approved. [90]
· Psilocybin: meaningful randomized depression evidence exists in structured research settings,
but the audited evidence does not support universal efficacy, superiority to standard antidepressants, or equivalence between trial protocols and state-regulated services; expectancy/blinding, acute adverse effects, durability, and generalizability remain important limitations. [91]
· Ibogaine: federal Schedule I status is separate from its emerging human evidence; the audited
benefit evidence is observational and cannot establish efficacy, while clinically important QT-prolongation and ventricular-arrhythmia risk requires prominent medical-safety scrutiny, especially when evaluating programs outside ordinary U.S. clinical pathways. [92]
· Clinical trials: a research-access pathway rather than a single modality; evidence maturity
depends on the specific intervention and study design, and registry listing alone is neither FDA approval nor independent proof of efficacy. [15]
The comparison becomes most useful when it directs the reader to the next question—what exact product or substance is involved, what evidence applies to that formulation and indication, what regulatory model governs access, and what screening, monitoring, provider scope, and follow-up the specific pathway provides. [93]
4.6 What the evidence can—and cannot—tell a prospective
patient
Evidence quality is not a single score. A randomized trial can provide stronger causal evidence for a defined intervention than an uncontrolled observational study, but even a well-conducted trial answers a bounded question. Its results depend on who was enrolled, how the intervention was delivered, what comparator was used, how outcomes were measured, and how long participants were followed. [83]
This matters especially in psychedelic research because the intervention is often difficult to mask. Participants may recognize distinctive psychoactive effects, which can influence expectations and make conventional blinding less effective. Researchers have proposed stronger masking assessments, active comparators, expectancy measurement, independent raters, and other methodological improvements. The presence of this problem does not justify dismissing the entire evidence base, but it does mean that effect estimates should be interpreted with more nuance than a simple “drug beat placebo” headline suggests. [94]
Supportive context creates another interpretive challenge. Many psilocybin trials include preparation, support during dosing, and post-session contact. Ketamine studies and real-world ketamine services vary in whether psychotherapy is integrated into treatment. State-regulated psilocybin services use their own facilitation structures. If a study evaluates a package, the result supports that studied package; it may not isolate the independent contribution of every component. [95]
For readers, the practical implication is to match the claim to the design. “A randomized trial found improvement under this protocol” is different from “this substance works for everyone.” “Participants improved after an observational program” is different from “the intervention caused the improvement.” “A product is FDA approved for a defined indication” is different from “all formulations of the same molecule are approved.” Precision protects both enthusiasm and skepticism from outrunning the evidence. [96]
4.7 Durability is a separate question from acute response
Psychedelic-related interventions are often discussed in terms of rapid change, but rapid response and durable benefit are different outcomes. A study that demonstrates improvement over days or several weeks does not automatically establish how long benefit persists, whether retreatment is needed, or what maintenance strategy is best. [97]
Esketamine has responder-enriched randomized-withdrawal evidence addressing relapse prevention among people who had already responded or remitted, but that design applies to a selected maintenance population. Racemic ketamine has evidence supporting acute and repeated treatment in selected depression populations, while longer-term strategy remains less standardized. Psilocybin trials have reported follow-up over varying periods, but different designs, populations, support structures, and outcome measures make it inappropriate to infer one universal durability profile. [98]
Durability also should not be confused with the intensity of the acute experience. A profound or memorable subjective experience may be personally meaningful, but this gateway guide does not treat subjective intensity as a validated substitute for clinical outcome measurement. Likewise, the absence of a dramatic experience does not by itself establish treatment failure. The evidence should be read through the outcomes the study actually measured rather than through cultural expectations about what psychedelic healing is supposed to feel like. [99]
4.8 Evidence maturity and regulatory maturity can move at
different speeds
Scientific evidence and legal access do not necessarily develop together. A substance can have promising clinical research while remaining investigational under federal law. A state can authorize a regulated service model without creating FDA approval. An FDA-approved product can have a clearly defined regulatory pathway while important comparative, maintenance, or real-world questions remain open. [62]
Psilocybin is a clear example. Randomized depression studies support serious scientific interest, while federal scheduling remains separate and Oregon and Colorado have developed state-regulated access systems that are not FDA prescription pathways. Ibogaine illustrates a different combination: human benefit evidence remains limited and observational, federal Schedule I status remains in place, and Colorado’s 2026 legislation creates a conditional research-pilot mechanism rather than routine treatment access. [100]
These combinations can be confusing to consumers because words such as “legal,” “approved,” “regulated,” “studied,” and “available” may all be true in different senses. The safest editorial practice is to name the exact sense every time. Legal under which authority? Approved for which product and indication? Regulated by which agency? Studied in what population and design? Available through which pathway? [62]
4.9 Comparing safety requires attention to what was actually
measured
Safety comparisons across modalities are especially vulnerable to overstatement. Trials may differ in how adverse events are elicited, how long participants are followed, what populations are excluded, and what monitoring is available. A low rate of serious events in a selected, intensively monitored research sample cannot automatically establish the same risk in a broader commercial population. [101]
For psilocybin, randomized-trial meta-analysis provides useful estimates for several common acute adverse effects, while broader reviews identify limitations in adverse-event reporting and longer-term certainty. For ketamine and esketamine, trial evidence and product labeling identify acute dissociation, sedation, blood-pressure effects, and other concerns, but comparisons between the two can be indirect. For ibogaine, the evidence base is smaller, yet the cardiac electrophysiology and case literature supports a particularly serious concern about QT prolongation and ventricular arrhythmias. [102]
This is why a single “safety ranking” would be misleading. Frequency, severity, detectability, reversibility, and the ability of a setting to respond are different dimensions. A relatively common transient adverse effect and a rarer potentially catastrophic event should not be treated as equivalent simply because both appear in an adverse-event table. The relevant safety question is what risks are known for the specific intervention and how the actual care system screens, monitors, and responds to them. [103]
4.10 Why deeper modality guides are still necessary
A gateway article can compare the landscape, but it cannot responsibly answer every modality-specific question without becoming several articles at once. Ketamine and esketamine require deeper treatment of formulations, routes, indications, evidence, maintenance, monitoring, and compounded products. Psilocybin requires separate treatment of research evidence, federal status, Oregon and Colorado service systems, psychological support, and emerging regulatory developments. Ibogaine requires deeper attention to cardiac risk, screening and monitoring questions, evidence limitations, international program evaluation, and developing research pathways. [104]
The role of this section is therefore to help readers recognize the correct branch of the decision tree. Once the reader knows which modality and access model they are investigating, the corresponding deeper guide can provide substantially more detail without forcing unrelated readers through every technical issue. This is also why internal links are part of the article’s safety and educational architecture rather than decorative additions.
4.11 Ketamine-assisted psychotherapy is not synonymous with
ketamine treatment
Ketamine-assisted psychotherapy, often abbreviated KAP, describes a model in which ketamine is incorporated into a psychotherapeutic process. That is conceptually different from saying that ketamine itself is psychotherapy or that every ketamine administration includes psychotherapy. The audited evidence and professional guidance used in this gateway article support keeping the pharmacologic intervention, the route and formulation, and the psychological treatment model analytically separate. [105]
This matters because a clinic may use the phrase “ketamine therapy” to describe medication treatment, KAP, or a broader package of services. Readers should ask whether psychotherapy is actually being delivered, who delivers it, what license that person holds, whether the psychotherapy occurs before, during, or after administration, and what evidence supports the particular combined model. [18]
The existence of evidence for IV ketamine’s short-term antidepressant effects does not independently validate every KAP framework, and the existence of psychotherapy within a ketamine program does not make a compounded or off-label formulation FDA approved. [106]
4.12 Route and formulation are part of the intervention
Psychedelic discussions often treat a molecule as if evidence follows the name regardless of how it is delivered. That is not a safe assumption. Route can change pharmacokinetics, onset, duration, monitoring needs, patient experience, and the evidence available for a particular protocol. Formulation can also change regulatory status. [107]
SPRAVATO is a specific intranasal esketamine product. Ketamine injection has its own approved labeling. Compounded ketamine products are not FDA approved. Evidence from monitored IV racemic ketamine studies should therefore not be generalized automatically to oral, sublingual, intranasal compounded, or other routes. [108]
For readers, this means the question “Does ketamine work?” is too broad for provider evaluation. The useful question is which ketamine or esketamine product, which route, for which indication, under what protocol, and supported by which evidence.
4.13 Short-term efficacy does not settle long-term management
The distinction between induction, repeated treatment, continuation, and maintenance deserves attention because these phases answer different questions. A treatment may produce a rapid response without establishing how long that response lasts or how frequently retreatment should occur. [109]
Esketamine’s randomized-withdrawal evidence provides information about relapse prevention among prior responders and remitters, but it should not be interpreted as a universal maintenance schedule for all patients. Racemic ketamine studies and guidance show meaningful short-term evidence alongside less standardized longer-term strategy. [110]
Commercial programs may package a predetermined number of sessions. Such packages can be operationally convenient, but the number itself should not be described as scientifically mandatory unless evidence supports that exact protocol. Readers can ask how response is assessed, what determines continuation, and what happens when expected benefit does not occur.
4.14 Psilocybin trial results belong to selected research
populations
Randomized psilocybin studies have produced important findings, but trial participants are selected through inclusion and exclusion criteria and treated under structured research conditions. Those features can improve safety and interpretability while limiting generalization to people with different diagnoses, medical histories, medications, social circumstances, or levels of clinical complexity. [111]
This is not unique to psychedelics, but it is especially important when public discussion moves quickly from a trial result to broad statements about who should use psilocybin. A positive study in major depressive disorder does not establish effectiveness for every psychiatric condition, and a trial exclusion does not automatically become a universal contraindication. [112]
Research support structures also matter. Preparation, dosing-session support, therapist or monitor contact, and follow-up vary among studies. A commercial or state-regulated program that uses the same substance may not reproduce those structures. [26]
4.15 Psilocybin evidence should not be reduced to a single
headline trial
The three depression trials discussed in this article illustrate why multiple studies matter. One randomized trial found greater symptom reduction with a single 25-mg psilocybin dose plus psychological support than with niacin placebo plus support. Another immediate-versus-delayed design reported large improvements but could not isolate drug effects from the broader treatment package. A direct comparison with escitalopram did not show a statistically significant difference on the prespecified primary depression outcome, despite several secondary outcomes favoring psilocybin. [27]
Taken together, these studies support serious evidence of antidepressant potential while also showing why claims of universal efficacy or superiority would be premature. They differ in comparator, treatment structure, sample, and outcome interpretation. [27]
A mature educational article should preserve those differences rather than selecting only the most favorable result. The goal is not to weaken the case for research; it is to describe the case accurately.
4.16 Functional unblinding is a methodological problem, not a
verdict
Psychedelic effects can make it difficult for participants and sometimes study personnel to remain unaware of treatment assignment. That can influence expectancy, behavior, reporting, and rating. Methodological reviews identify this as a recurring challenge and recommend better measurement and design strategies. [94]
It would be equally misleading to ignore the issue or to claim that it proves psychedelic benefits are placebo effects. The audited evidence does not quantify how much observed benefit is explained by expectancy across the field. The appropriate conclusion is narrower: masking limitations reduce certainty about effect magnitude and should be considered alongside other evidence. [94]
This distinction is useful for readers because polarized discussion often treats expectancy as either irrelevant or fatal to the science. Neither position reflects the audited source record.
4.17 Acute adverse effects and serious adverse events are
different categories
Safety communication improves when common acute effects are distinguished from less common but potentially serious events. In psilocybin trials, meta-analytic evidence identifies increased acute risks such as headache, nausea, anxiety, dizziness, and elevated blood pressure. Broader reviews identify serious and medically significant events as uncommon in monitored studies while also noting limitations in adverse-event ascertainment. [84]
These findings should not be translated into either “psilocybin is harmless” or “psilocybin is dangerous.” They describe a safety profile under studied conditions. Real-world risk can differ when populations, products, screening, dose, setting, co-use, or monitoring differ.
The same principle applies to ketamine and esketamine. Dissociation, sedation, dizziness, nausea, and blood-pressure effects are not equivalent in severity to every possible serious complication, and product-specific labeling should control descriptions of approved esketamine risks. [113]
4.18 Ibogaine requires a different balance of benefit and risk
discussion
The ibogaine section cannot responsibly mirror the tone used for psilocybin or esketamine because the evidence base is different. The audited veteran cohort is promising but uncontrolled. It documents improvement after treatment in a selected group, not causal efficacy. [47]
The cardiac-risk evidence, by contrast, spans clinical review, mechanistic evidence, and a severe human case. This creates an asymmetry: benefit claims require strong qualification while cardiac safety deserves prominent, concrete attention. [85]
This does not mean that research should stop or that every person exposed to ibogaine will experience a serious arrhythmia. The sources do not provide a reliable population-wide incidence. It means that a program’s medical infrastructure and cardiac-risk management cannot be treated as secondary details. [114]
4.19 Screening cannot make ibogaine risk-free
Programs may describe ECG screening, laboratory testing, medication review, electrolyte assessment, or onsite monitoring. Those practices may be relevant to risk management, but the audited evidence does not establish a screening algorithm that eliminates ibogaine’s cardiac risk. [85]
Readers should therefore be cautious when a program uses screening as proof of safety. The meaningful questions include who interprets cardiac information, what monitoring occurs during and after administration, what medications or substances are reviewed, what emergency treatment is available, and how rapidly a participant can be transferred if needed. [114]
Because this gateway article does not audit individual international programs, it cannot certify that any specific program meets an adequate standard. That evaluation belongs in a deeper ibogaine guide using current jurisdiction- and program-specific evidence.
4.20 Research participation is not a workaround for ordinary
treatment eligibility
People may view clinical trials as another way to “get” a promising psychedelic treatment. That framing can obscure the purpose of research. A study enrolls participants to answer a scientific question under protocol-defined conditions. Eligibility can be narrow, assignment may be randomized, and the experimental intervention may not be guaranteed. [15]
Research teams also may require procedures that would not be part of ordinary treatment, and participants may be asked to contribute data after the intervention. Informed consent should make these features clear. [45]
A registry listing can help a reader locate studies and understand protocol metadata, but it should not be treated as endorsement, approval, or proof of benefit. [87]
4.21 Evidence should be updated without chasing novelty
Psychedelic research is fast moving, which creates pressure to treat the newest study as the most important. Currentness matters, especially for regulatory status, labeling, and emerging safety signals, but novelty is not the same as evidentiary strength.
A new uncontrolled study should not automatically displace an older high-quality randomized trial. A new review should be evaluated for methods and scope. A regulatory announcement should be distinguished from an effective rule or approved product. The source hierarchy used for this article is designed to preserve that discipline.
For publication, time-sensitive controlling sources should be reopened and verified. The broader evidence synthesis should change when new evidence materially alters a claim, not merely because a newer citation exists. Related Psychedelist guides
[Internal link forthcoming: A Guide to Ketamine Therapy and Esketamine Treatment] [Internal link forthcoming: A Guide to Psilocybin Treatment, Services and Clinical Research] [Internal link forthcoming: A Guide to Ibogaine Treatment Programs and Medical Safety]
These deeper guides are intended to extend, not replace, the distinctions established in this gateway article. Until a guide is published, the placeholder should remain non-clickable rather than being converted into an invented URL.
5. What the care journey may involve
 Responsible care
usually involves much more than the administration session itself.
A responsible psychedelic-related care process is usually more than the administration session itself. Depending on the pathway, it may begin with an inquiry or referral, move through eligibility review and screening, include preparation and informed consent, proceed to administration or another protocol-defined intervention, and continue through observation, discharge, follow-up, integration, referrals, or longer-term care. The sequence, terminology, and responsible professional differ across FDA-regulated medication treatment, state-regulated services, clinical trials, and international programs; no single sequence should be treated as universal. [115]
This section describes common stages readers may encounter. It is not a universal protocol, and the presence of these stages does not by itself establish that a particular program is medically adequate, evidence-based, or appropriate for an individual.
5.1 Inquiry, orientation and eligibility
The first contact may be an intake request, referral, consultation, service inquiry, or research prescreen. What should become clear at this stage is the nature of the pathway: whether the person is exploring an FDA-regulated medication treatment, a state-regulated service, a research protocol, or another program; who provides it; what formal entry requirements apply; and what evaluation steps come next. The exact intake process is pathway-specific. [116]
Eligibility is not the same thing across these models. In a clinical trial, eligibility is protocol-defined. In Oregon and Colorado regulated-service systems, entry and screening requirements arise from their own statutes and rules. In FDA-regulated medication care, product labeling and individualized clinical assessment govern the relevant medical questions. Meeting one pathway’s criteria should therefore not be treated as general medical clearance for psychedelic-related care. [69]
5.2 Medical and psychological screening
Screening is intended to identify information that may affect eligibility, risk, monitoring, referral needs, or whether the proposed pathway can appropriately serve the person. Depending on the model, this may include medical and psychiatric history, current symptoms, medication and substance use, cardiovascular or other health considerations, and other factors specified by the applicable product label, research protocol, or state rules. [117]
The depth and purpose of screening vary. An FDA-regulated medication pathway operates under product-specific requirements; Oregon and Colorado regulated services operate under their own state rules; and clinical trials use protocol-defined eligibility and safety criteria. Research exclusions and state-program screening rules should not be converted into universal clinical contraindications outside the framework that created them. [118]
Medication review is particularly important because concomitant drugs can alter psychedelic effects in different directions, and changing or discontinuing psychiatric medication can itself carry risk. The evidence is substance- and medication-specific, so possible interactions should be evaluated by qualified professionals rather than converted into universal stop rules or self-directed tapering instructions. [119]
5.3 Informed consent and expectations
Informed consent should occur before the intervention, not after a person is already committed to proceeding. The details depend on the care model, but consent should make understandable the nature and purpose of what is being offered, material risks and uncertainties, what participation entails, the provider’s role and relevant boundaries, and the applicable opportunities to ask questions, decline, or withdraw. In psychedelic clinical-care ethics, expectation-setting itself also deserves attention because the way an intervention is framed may shape experience. [120]
For research, consent is an ongoing voluntary process and does not guarantee therapeutic benefit or assignment to an experimental intervention. [45] Oregon and Colorado use their own state-specific consent and service requirements; those requirements do not define research consent or conventional medical consent. [65] Consent therefore should be evaluated within the actual pathway rather than treated as one generic psychedelic-care document.
Expectations also deserve attention. Ethical consent should leave room for intense or transformative experiences, nonresponse, disappointment, and uncertainty rather than promising a breakthrough, cure, mystical experience, or particular emotional result. Research outcomes are population-level findings, not predictions for an individual. [121]
5.4 Preparation
Preparation can include practical orientation to the setting and process, discussion of communication and boundaries, clarification of who will be present and what their roles are, and planning for support or follow-up. Oregon and Colorado define preparation within their regulated service models, while psychedelic clinical research has used varied psychological-preparation approaches. Those structures should be described within their own frameworks rather than treated as one universal preparation protocol. [122]
Preparation is not standardized across psychedelic-related care. Studies differ in the amount, timing, and type of psychological support they provide, and current evidence does not establish one universally validated preparation or psychotherapy model. Preparation, facilitation, and integration also should not automatically be labeled psychotherapy unless the provider’s actual license, scope, and service support that description. [123]
5.5 Administration, supervision and monitoring
The administration stage differs sharply across pathways. SPRAVATO is administered under its current FDA labeling and REMS framework, with product-specific supervision and monitoring requirements. [34] Off-label racemic ketamine care can involve different routes and clinical protocols, and evidence from monitored IV research should not be transferred automatically to other delivery models. [56] Oregon and Colorado regulate administration within their respective state service systems rather than through ordinary prescription treatment. [124] A clinical trial follows its protocol. [125]
These distinctions matter because the word “supervised” is incomplete without details. Readers should understand who is present, what that person is licensed or authorized to do, what observations or clinical monitoring occur, how distress or a medical problem would be handled, and what emergency resources are available. The answer depends on the product, protocol, and jurisdiction rather than on the label “supervised” alone. [126]
The level of monitoring should not be inferred from décor, branding, the use of the word “clinic,” or the mere presence of someone with a healthcare credential. The relevant question is what monitoring and emergency capability the specific intervention and setting actually provide.
5.6 Observation, discharge and transportation
The end of drug administration is not necessarily the end of the care episode. Some pathways require defined observation or discharge procedures, while others use jurisdiction-specific safety and transportation planning. Current SPRAVATO requirements include at least two hours of post-administration monitoring, while Oregon’s regulated system uses its own safety, support, and transportation forms and requirements. These examples should not be generalized to every modality. [127]
A reader should know before the session what post-administration observation applies, how discharge or release is determined, what transportation or activity restrictions apply, whom to contact if concerns emerge afterward, and when escalation to emergency care is appropriate. Those requirements should come from the applicable product label, clinician, regulator, study protocol, or program—not from a generalized psychedelic checklist. [128]
5.7 Integration, follow-up and continuity of care
Post-session support can be described as integration, follow-up, aftercare, clinical reassessment, study follow-up, or another term depending on the model. These are not necessarily equivalent services. The integration literature describes varied therapeutic frameworks and does not establish one standardized integration method as independently responsible for clinical benefit. Integration also should not automatically be treated as synonymous with psychotherapy. [31]
Follow-up can serve different purposes. In medical care it may include assessment of response, adverse effects, medication decisions, or referral; in research it is protocol-defined; and in state-regulated services it remains bounded by the facilitator’s authorized scope and the applicable state rules. The important question is whether responsibility after the acute experience is clear and whether needs outside the program’s scope can be referred appropriately. [129]
Continuity also includes knowing where responsibility begins and ends. A facilitator, prescribing clinician, psychotherapist, research team, primary-care clinician, and emergency service may hold different roles and authorities. A program does not need to provide every service internally, but it should be possible to identify its scope, its follow-up responsibilities, and how referral or escalation occurs when needs extend beyond that scope. [130]
5.8 Records, privacy and coordination
Records and privacy practices depend on the pathway and governing framework. Oregon’s psilocybin rules address client records and related service requirements, while Colorado’s regulated natural-medicine system has its own operational and recordkeeping rules. Research participants receive study-specific information through the protocol and consent process. These requirements are not interchangeable and should not be generalized across settings. [131]
Before proceeding, readers may want to understand what information is collected, who can access it, how consent and session records are maintained, whether information may be shared with another clinician or support professional, and how they can obtain information about applicable privacy practices. Where coordination with existing healthcare is relevant, the roles and permissions for that coordination should be clear.
Across all of these stages, the central principle is consistency between the claimed care model and the process actually delivered. FDA-regulated medication treatment should be evaluated under its product-specific medical and regulatory framework. A state-regulated service should be evaluated under the rules of that state. A clinical trial should be understood as protocol-governed research. An international program requires jurisdiction-specific verification rather than assumptions based on marketing language. The sequence may look different in each case, but readers should be able to identify who is responsible at each stage, what safeguards actually apply, what happens next, and where responsibility ends. [132]
5.9 The care journey is also a chain of handoffs
One of the easiest ways to misunderstand psychedelic-related care is to imagine a single provider carrying responsibility from the first inquiry through long-term follow-up. Some programs do offer highly integrated care, but many pathways involve several people or organizations. A referring clinician, prescribing clinician, facilitator, therapist, research coordinator, study physician, service center, laboratory, pharmacy, emergency department, or outside specialist may each hold a different part of the process. [133]
That makes handoffs an important quality question. A handoff does not need to be elaborate, but responsibility should not disappear between stages. If screening identifies a concern outside the program’s scope, the participant should know whether the program pauses, declines, seeks consultation, or refers. If an adverse effect appears after administration, the participant should know whom to contact. If the acute program ends but ongoing psychiatric care is still needed, the boundary between the psychedelic program and the person’s usual treatment should be understandable. [129]
In research, the protocol and consent process help define these responsibilities. In ordinary medical care, professional practice and the treatment relationship shape them. In state-regulated services, statutes and rules define important parts of the facilitator and service-center role. These systems should not be merged into a single standard, but all can be evaluated for whether the participant can tell who is responsible for what. [134]
5.10 Preparation should clarify process, not script the experience
Preparation is often described as a way to orient participants to what may happen, establish communication and boundaries, and reduce avoidable uncertainty. The audited literature shows substantial variation in psychological support and psychotherapy models used in psychedelic research. That variation argues against presenting a single preparation script as scientifically required. [31]
A useful distinction is between process preparation and outcome suggestion. Process preparation can explain the setting, approximate time commitment, who will be present, how the participant can communicate needs, what physical contact policies apply, what happens if they become distressed, and how the session ends. Outcome suggestion goes further by implying that the person should have a mystical breakthrough, recover a particular memory, confront trauma in a particular way, or interpret difficult material according to the provider’s preferred framework. Ethics concerns about expectancy and vulnerability make that distinction important. [135]
Preparation can also establish consent around features that may become difficult to negotiate during an altered state. Touch, recording, observers, communication with family or support people, and emergency procedures should not first become clear after administration begins. Oregon’s written-consent requirements for supportive touch are one jurisdiction-specific example of formalizing advance boundaries. [136]
5.11 Administration is where pathway differences become most
visible
The acute session may be the most visible part of psychedelic-related care, but even here the same words can conceal very different systems. Direct observation under a product-specific REMS, monitored off-label medical treatment, facilitator-supervised state services, and protocol-governed research are not interchangeable forms of “sitting with” a participant. They differ in authority, monitoring, documentation, emergency procedures, and what the person present is trained and permitted to do. [137]
The distinction between supportive presence and clinical monitoring is especially important. A person can be emotionally attentive without performing medical monitoring, and a clinician can perform physiologic monitoring without providing psychotherapy. Some models combine functions; others separate them. Readers should look for the actual roles rather than assuming that the presence of a therapist, nurse, physician, facilitator, or guide automatically answers every safety and support question. [138]
The physical setting can influence comfort and experience, but environmental aesthetics should not be used as evidence of clinical quality. A calm room, music, eye shades, or other supportive features may be part of a protocol or program, yet they do not substitute for appropriate screening, professional scope, emergency readiness, or evidence supporting the intervention. Conversely, a conventional medical setting does not by itself prove that every treatment offered there is FDA approved or supported by the same evidence. [139]
5.12 Follow-up should match the claims a program makes
The more a program presents itself as treating a psychiatric or medical condition, the more important it becomes to understand how outcomes and adverse effects are assessed after the acute session. This does not mean every model must provide indefinite longitudinal care. It means the promised service and the actual follow-up should be coherent. [140]
A program that describes itself primarily as a regulated facilitation service may have a different follow-up role from a psychiatric practice managing treatment-resistant depression. A research site follows participants according to protocol rather than necessarily assuming their ordinary clinical care. An international program may provide an aftercare plan but have limited ability to evaluate a participant once that person returns home. These differences should be disclosed rather than blurred by the generic word “integration.” [141]
Follow-up can include response assessment, adverse-event review, medication management, integration-oriented discussion, referral, or coordination with existing care, but those functions should be named accurately. The evidence does not support treating integration as a universal cure-enhancing mechanism, and a supportive conversation should not be relabeled psychotherapy unless the provider and service actually meet that description. [142]
5.13 What a coherent care journey looks like
A coherent pathway is one in which each stage logically connects to the next. The intervention offered matches the pathway described. Screening matches the foreseeable risks. Consent matches the actual service. Preparation establishes realistic expectations and boundaries. Supervision matches the provider’s role and the intervention. Discharge occurs under the applicable rules or clinical judgment. Follow-up and referral responsibilities are defined. Records and privacy practices match the governing framework. [143]
This coherence is more informative than whether a program copies every feature of a well-known research trial. Research protocols are designed for research, state programs are designed under state law, and medical practices operate within clinical and professional regulation. Responsible care does not require them to look identical. It requires them to be internally consistent, transparent about their authority and limits, and proportionate to the risks and claims of the intervention being offered.
6. Screening, contraindications, consent, and safety
planning
 Screening and safety
planning are individualized professional processes, not self-clearance checklists.
Screening is not a formality and it is not a questionnaire that allows a person to determine for themselves that psychedelic-related care is safe. Its purpose is to identify information that may affect eligibility, change risk, require additional evaluation, alter monitoring or setting, or make a particular pathway inappropriate. What matters depends on the exact substance or formulation, route, indication, individual history, and governing care model. [144]
For that reason, the considerations below are categories for discussion with qualified professionals, not a self-clearance checklist. A product-label contraindication, a research exclusion, a state-program rule, and a clinician’s individualized risk judgment are different kinds of authority and evidence. A restriction from one pathway should not be silently transferred into another. [118]
6.1 Psychiatric history and current mental state
Psychiatric screening may include current symptoms, diagnoses, prior treatment, substance-use history, acute safety concerns, and other history relevant to the proposed intervention. Professional guidance and state rules identify psychiatric risk factors that can affect eligibility, referral, or level of evaluation, but they do not establish one universal contraindication hierarchy across psychedelic-related pathways. [145]
This distinction is especially important because psychedelic clinical trials commonly enroll selected, medically and psychiatrically screened populations. Study eligibility criteria help define and protect the research population; they do not automatically establish universal contraindications for routine medical care or state-regulated services. Positive findings from carefully selected participants also should not be assumed to apply unchanged to populations that were excluded. [146]
The provider’s professional scope also matters when significant psychological distress or instability is identified. Oregon and Colorado facilitators operate within state-defined roles, and a facilitator credential or other supportive role should not be assumed to substitute for psychiatric evaluation, crisis services, or emergency care unless the provider has the separate authority and resources to perform those functions. [70]
6.2 Cardiovascular and other medical considerations
Physical-health screening should be tied to the known and plausible risks of the specific intervention. For SPRAVATO, the current label contains product-specific contraindications, warnings and precautions involving blood pressure and cardiovascular or cerebrovascular risk, together with required assessment and monitoring. Those requirements govern SPRAVATO and should not be generalized to other psychedelic modalities or ketamine formulations. [34]
Ibogaine illustrates why modality-specific screening matters especially strongly. Current review evidence identifies QT prolongation and potentially life-threatening ventricular arrhythmias associated with ibogaine and noribogaine, with mechanistic and human case evidence providing corroboration. That evidence makes cardiovascular assessment, medication/substance review, monitoring, and emergency readiness central questions; it does not show that any screening protocol can eliminate the risk. [85]
Other medical conditions may also affect suitability or require additional evaluation depending on the intervention. The appropriate significance of a condition belongs with clinicians qualified to interpret the person’s history in relation to the proposed substance, formulation, route, and setting rather than with a generalized online checklist. [147]
6.3 Pregnancy and reproductive considerations
Pregnancy and breastfeeding illustrate why pathway-specific sourcing is necessary. The current SPRAVATO label warns of embryo-fetal toxicity and states that breastfeeding is not recommended. Oregon’s psilocybin rules use a different framework: when a client reports pregnancy or feeding with breast milk, the facilitator must inform the client that the risks of consuming psilocybin in that circumstance are unknown. These statements apply to their respective pathways and should not be generalized across other substances or services. [148]
A research protocol may also impose its own pregnancy-related eligibility requirements, but study criteria remain protocol-specific. People with pregnancy, breastfeeding, or other reproductive questions should receive individualized guidance from an appropriately qualified healthcare professional, while current product labeling or controlling state rules should govern any pathway-specific statement. [149]
6.4 Medications, supplements, alcohol and other substances
Medication and substance review is a core safety function because concerns can be pharmacologic, physiologic, psychiatric, or protocol-specific. Human interaction evidence shows that concomitant medications can attenuate, potentiate, or produce no detected change in classic-psychedelic effects depending on the drug and context; the evidence is too heterogeneous for one universal interaction rule. [119]
The existence of a potential interaction does not justify changing treatment independently. Medication tapering or discontinuation can itself produce withdrawal or discontinuation effects or psychiatric relapse, and a research washout rule is a study requirement rather than a general-purpose medication instruction. Medication changes should be handled with the relevant prescribing clinician and treatment team. [150]
State service rules can add another layer without becoming universal pharmacology. Colorado’s facilitator rules, for example, create referral, medical-clearance, or consultation pathways around specified medication-related risks; Oregon uses its own client-information and consultation framework. Those are jurisdiction-specific regulatory requirements, not proof that the same medication rule applies across ketamine, esketamine, psilocybin, ibogaine, or investigational compounds. [151]
6.5 Capacity, consent and boundaries
Valid consent requires more than a signed form. Before participation, a person should have a meaningful opportunity to understand the nature and purpose of the intervention or service, important risks and uncertainties, what participation entails, relevant alternatives where applicable, and the limits of the provider’s role. In research, informed consent is voluntary and ongoing and does not guarantee therapeutic benefit. [152]
State-regulated systems impose their own consent and conduct requirements. Oregon and Colorado regulate consent, facilitator conduct, safety processes, and service delivery within their respective frameworks. Those requirements should be described as jurisdiction-specific rather than treated as a universal national consent standard. [68]
Because altered states can increase vulnerability, professional boundaries should be established before administration. Ethics guidance supports explicit touch and boundary policies, and Oregon requires prior written consent before a facilitator uses supportive touch. That does not mean supportive touch is necessary or clinically beneficial; it means the role, limits, consent process, and continuing right to refuse should be clear before the participant is in an altered state. [153]
6.6 Support and emergency planning
Safety planning should be tied to the actual pathway rather than treated as one generic psychedelic protocol. FDA guidance addresses monitoring and emergency readiness in investigational psychedelic trials; SPRAVATO has product-specific monitoring and discharge requirements; and Oregon requires its own service-center emergency, safety/support, and transportation processes. These frameworks illustrate different responsibilities and should not be treated as interchangeable standards. [154]
Emergency readiness should be evaluated separately from routine emotional support or integration. A calm setting, facilitator experience, or post-session support does not by itself establish the ability to recognize and respond to an acute medical or psychiatric emergency. This distinction is especially important for ibogaine, where the audited cardiac-safety evidence supports prominent attention to monitoring and emergency capability. Programs should be evaluated according to the risks of the intervention and the actual capabilities available at the site. [155]
The same principle applies after the participant leaves. A responsible pathway should make clear what follow-up it provides, whom to contact for routine concerns, when referral to another clinician is needed, and when urgent or emergency services fall outside the program’s own scope. The exact responsibilities depend on the care model and governing rules. [156]
Screening and safety planning are therefore best understood as professional risk-management processes, not a self-clearance exercise and not a guarantee of safety. Structured screening can identify concerns, improve informed decision-making, and clarify when additional evaluation, referral, or a different setting may be needed, but it cannot make a psychoactive intervention risk-free. Medical, psychiatric, medication, pregnancy-related, and other individualized safety questions should be evaluated by appropriately qualified clinicians in relation to the specific intervention being considered. [157]
6.7 Why screening standards cannot simply be copied from
research
Research protocols often use detailed inclusion and exclusion criteria because investigators are trying to answer a defined scientific question while managing participant safety and interpretability. Those criteria may exclude people with particular diagnoses, medications, medical histories, substance-use patterns, pregnancy potential, or other characteristics. The existence of an exclusion can be clinically informative, but it does not automatically transform the exclusion into a permanent contraindication for every form of psychedelic-related care. [125]
This distinction matters in both directions. A person who would be excluded from a particular trial should not infer that every possible pathway is necessarily unsafe, and a person who would qualify for a trial should not infer that they have been broadly “cleared” for psychedelic treatment. Trial eligibility is protocol eligibility. Clinical suitability is an individualized professional judgment made within the actual treatment or service framework. [158]
The same caution applies to state-regulated service rules. Oregon and Colorado establish screening, referral, consent, and service requirements for their own regulated systems. Those rules can be useful examples of how jurisdictions operationalize safety, but they are not national medical-practice standards and should not be used to override product labeling or individualized clinical assessment in a different pathway. [57]
6.8 Risk is dynamic rather than a one-time intake result
Screening occurs before an intervention, but risk can change. New medications may be started, doses may change, substance use may change, a medical condition may emerge, psychiatric symptoms may worsen, pregnancy status may change, or a participant may arrive for a session in a state that differs from the original assessment. Responsible systems therefore need a way to recognize when previously collected information is no longer sufficient. [159]
Different pathways handle reassessment differently. A medication clinic may reassess symptoms, vital signs, adverse effects, or medication changes across visits. A research protocol may require scheduled safety assessments and reporting. A state-regulated service may impose its own pre-session checks and facilitator responsibilities. The precise procedure should come from the governing pathway; the broader principle is that an intake form completed weeks earlier cannot substitute for attention to clinically meaningful changes. [160]
This is one reason promises of “medical clearance” should be interpreted carefully. Clearance is not a guarantee that an adverse event cannot occur. It is a decision made from available information at a particular time within a particular professional and regulatory framework. Good screening reduces avoidable uncertainty and identifies when more evaluation is needed, but it does not eliminate the inherent uncertainty of psychoactive treatment or service delivery. [103]
6.9 Psychological vulnerability and the treatment environment
Medical safety is only part of the risk picture. Psychedelic experiences can involve intense affect, fear, confusion, altered perception, suggestibility, or a temporary reduction in ordinary orientation and control. The clinical significance of those experiences varies by substance, dose, person, and setting, and this guide does not attempt to predict an individual response. It does mean that the interpersonal and environmental structure around the intervention is relevant to safety. [161]
Expectation-setting should therefore avoid both alarmism and romanticization. Describing every difficult experience as therapeutic can discourage participants from reporting harm, while describing all distress as evidence of medical danger can misrepresent the range of acute psychedelic effects. A responsible provider should be able to explain what kinds of experiences may occur, how distress is supported, when clinical escalation is needed, and how the participant’s preferences and boundaries will be respected. [162]
This is also where scope becomes important. Emotional support from a facilitator is not automatically psychotherapy, and psychotherapy is not emergency psychiatry. A provider may be highly skilled in one role while lacking authority or resources for another. The care system should make those boundaries visible before the participant enters an altered state. [163]
6.10 Adverse-event planning should include what happens after
the session
Acute monitoring receives much of the attention in psychedelic care, but not every concern appears during administration. Symptoms can emerge or become apparent after discharge, and some research protocols include follow-up specifically to capture later events and outcomes. The appropriate duration and type of follow-up are intervention-specific; the evidence does not support one universal post-psychedelic monitoring schedule. [164]
Readers can nevertheless evaluate whether a program has a defined route for post-session concerns. Who can be contacted? During what hours? What symptoms are within the program’s ordinary follow-up role, and what concerns should be directed to urgent or emergency care? How are adverse events documented? If the program is not equipped to manage a problem, is referral responsibility clear? These questions do not require the program to promise unlimited care. They require clarity about responsibility. [165]
Longer-term uncertainty should also be represented proportionately. Psilocybin safety reviews provide useful information about acute adverse effects and monitored-study events, but inconsistent ascertainment and relatively selected research populations limit precise estimates for rare or delayed harms. Ketamine and esketamine have their own evidence and product-specific concerns. Ibogaine’s cardiac risk requires a different level and type of scrutiny. A generic statement that “psychedelics are safe when supervised” would therefore be too broad for the source record. [166]
6.11 Safety claims should be auditable
Programs may use phrases such as “medically screened,” “doctor supervised,” “evidence based,” or “safe protocol.” Each phrase should be translated into something verifiable. Who performs the screening? What credential and scope do they hold? Which intervention-specific risks are evaluated? What monitoring is used? What equipment and trained personnel are available? What happens if transfer is necessary? Which evidence or regulatory requirement supports the protocol? [167]
The purpose is not to demand hospital-level infrastructure from every model. Different pathways legitimately have different requirements. The purpose is to make sure that the safety claim matches the pathway and the foreseeable risks. An FDA-regulated product should meet its product-specific requirements. A state-regulated service should meet its jurisdiction-specific requirements. A research study should follow its approved protocol. An international program should be evaluated against verifiable local authority and its actual medical capabilities rather than against marketing language. [168]
7. How to evaluate a clinic, service center, study, or
program
 Evaluating a provider
or program means looking beyond marketing language to credentials, scope,
evidence, safety systems, and accountability.
A polished website, testimonials, professional photography, or the use of words such as “clinical,” “medical,” or “therapeutic” can describe presentation, but they do not establish licensure, legal scope, evidence quality, or safety. A more useful evaluation starts by identifying the exact pathway and then checking whether the provider’s credentials, claims, supervision, safeguards, and follow-up match that pathway. [169]
7.1 Identify what the organization and provider actually are
First determine whether the organization is functioning as a medical practice, a state-regulated service center or healing center, a research site, or an international program. Then identify who performs each role: prescribing, medical screening, psychological assessment, facilitation, psychotherapy, administration-session supervision, emergency response, and follow-up. Specialized psychedelic training may be relevant to preparation and competence, but a course or private certificate is not the same thing as a professional license or legal authority to practice medicine or psychotherapy. [170]
Oregon and Colorado illustrate why this distinction matters. Oregon psilocybin facilitation remains a state-defined role even when a facilitator also holds a separate healthcare license. Colorado distinguishes Facilitators from Clinical Facilitators and ties clinical diagnosis and treatment to the person’s separate qualifying professional license. These rules are jurisdiction-specific, but the broader evaluation principle is transferable: verify the credential that authorizes the actual service being delivered rather than assuming authority from a title. [16]
7.2 Examine the screening process
A serious screening process should be understandable in structure even when the final clinical judgment is individualized. Readers can ask who reviews the intake information, what kinds of concerns trigger additional medical or behavioral-health evaluation, what can lead to referral or nonparticipation, and what professional scope the reviewer has. Research exclusions, product-label contraindications, and state-service screening rules should not be presented as interchangeable. [171]
The quality signal is not simply that a program has a questionnaire. It is whether the screening process is matched to the risks and authority of the specific intervention and whether the program has a clear response when a person falls outside its routine scope. [172]
7.3 Match evidence claims to the exact intervention
Claims such as “FDA approved,” “clinically proven,” “research backed,” or “high success rate” require specificity. Which product or formulation? Which indication? Which study population? Which route and setting? What comparator and follow-up period? An FDA approval for SPRAVATO does not transfer to racemic ketamine or compounded ketamine, and positive psilocybin trials do not establish the effectiveness of every state-regulated service or commercial program. [173]
The same caution applies to emerging evidence. The audited ibogaine cohort supports saying that substantial improvements were reported in a selected observational group, but it does not establish general efficacy or validate the facility where treatment occurred. [47] A responsible provider should be able to distinguish what is established, what is supported but limited, what is investigational, and what remains uncertain.
7.4 Understand supervision and emergency readiness
“Supervised” is not a complete safety description. For SPRAVATO, supervision and monitoring are product-specific regulatory requirements: administration occurs in certified healthcare settings under direct observation, with at least two hours of monitoring and other REMS-linked requirements. Those rules should not be generalized to racemic ketamine, psilocybin services, or other modalities. [34]
For other pathways, readers should identify who remains present, what observations or clinical monitoring occur, what the onsite team is trained and legally authorized to do, and how a medical or psychiatric emergency would be escalated. Oregon requires service-center emergency planning within its own regulated system. Ibogaine raises a different concern because current evidence supports a clinically important QT-prolongation and ventricular-arrhythmia risk; a program’s statement that it “screens carefully” is not proof that this risk has been eliminated. [174]
7.5 Review boundaries, touch, privacy, records, and
accountability before altered states
Professional boundaries should be clear before administration. Ethics guidance supports explicit policies on touch, sexual and romantic boundaries, privacy, recording, observers, and communication. Oregon separately requires prior written consent before supportive touch by a facilitator. These safeguards do not establish that supportive touch is necessary or beneficial; they establish the importance of advance consent and defined limits when participants may be unusually vulnerable. [136]
Safeguarding should not be treated as theoretical. A naturalistic survey has documented reports of sexual misconduct and other adverse experiences in psychedelic contexts, although it cannot establish prevalence in licensed clinical care. That evidence supports asking how a program vets providers, supervises staff, receives complaints, documents concerns, and identifies the regulator or professional body responsible for accountability. [175]
Privacy and record practices also depend on the framework. State-regulated services, healthcare practices, and research programs can operate under different documentation and disclosure rules. Readers should ask what records are created, who can access them, how information may be shared, and what complaint or reporting route applies rather than assuming that every setting operates like a conventional medical practice. [71]
7.6 Look beyond the administration session
Preparation and post-session support can be clinically meaningful parts of some models, but the terminology matters. Integration is described in the literature through diverse frameworks, and current evidence does not establish one standardized integration method as independently responsible for improved outcomes. Integration also should not automatically be called psychotherapy unless the provider’s license, scope, and actual service support that description. [31]
A useful evaluation therefore asks what follow-up is actually provided, who is responsible if symptoms worsen or a medical concern emerges, how referrals are handled, and whether the participant can transition back to ongoing healthcare when the program’s role ends. [140]
7.7 Understand the financial agreement before committing
Financial transparency is part of evaluating a program even though pricing structures vary. Readers should ask for an itemized explanation of professional fees, medication or product costs, facility charges, monitoring, preparation, follow-up, cancellation terms, refunds, and any travel-related expenses that are not included. In Oregon’s regulated system, current rules require specified fee, refund, additional-fee, and product-price information to be provided before money is collected; that is an Oregon-specific protection, not a universal rule for every psychedelic program. [176]
The strongest overall evaluation is not a score or ranking. It is consistency: provider credentials should match the role; evidence claims should match the evidence; screening and supervision should match the risks; boundaries should be established before vulnerability; emergency capability should match foreseeable complications; follow-up should be defined; and accountability should be verifiable.
7.8 Verify licenses and credentials through the issuing authority
A provider biography is a useful starting point, but it is not the final source for a regulated credential. When a service depends on professional licensure or a state psychedelic-service license, readers should verify the credential through the issuing authority where possible. The purpose is not suspicion for its own sake. Licenses can expire, change status, carry restrictions, or apply to a narrower role than a marketing page implies. [16]
Verification should also preserve the distinction between different credentials. A physician license, psychology license, counseling license, facilitator license, clinical-facilitator license, private training certificate, and research affiliation are not interchangeable. A provider may legitimately hold several at once, but each should be understood for the authority it actually conveys. [33]
When a program uses a team model, readers can ask which credential belongs to which team member and who is responsible for each function. The presence of one physician on an advisory board, for example, does not establish that the physician screens every participant or remains responsible during every administration session. “Medical team” should resolve into actual roles.
7.9 Ask who makes the final eligibility decision
Programs often describe screening as collaborative, but the final decision can rest with different people depending on the model. In medical treatment, a qualified clinician may determine whether treatment is appropriate within professional practice and product requirements. In research, investigators apply protocol eligibility. In state-regulated services, facilitators and other professionals operate under jurisdiction-specific rules. [160]
Readers should understand whether the person reviewing medical information has the authority and competence to interpret it. If a facilitator identifies a concern outside their scope, what consultation or referral process follows? If a commercial clinic uses a remote questionnaire, who reviews it and what happens when the answers are ambiguous? If an international program requests an ECG or laboratory result, who interprets it and what standard is used? [177]
The strongest signal is not a long intake form. It is a process that can recognize uncertainty and escalate it appropriately.
7.10 Examine how the program describes benefits
Responsible benefit claims are bounded. They identify the population, condition, intervention, and evidence level rather than promising generalized transformation. [178]
A clinic discussing esketamine should distinguish current approved indications from broader claims about ketamine or psychedelics. A ketamine clinic should distinguish evidence for monitored IV racemic ketamine from claims about compounded or at-home routes. A psilocybin service should not imply that state authorization proves treatment efficacy for depression. An ibogaine program should not convert observational improvement in a selected veteran cohort into a general cure claim. [179]
Testimonials deserve similar caution. Personal stories can communicate lived experience, but they cannot establish average effectiveness, comparative superiority, or safety. Selection is rarely systematic, negative outcomes may be underrepresented, and the person reading the story usually cannot know how similar the storyteller’s clinical circumstances were to their own.
Readers can also notice whether a program discusses nonresponse and uncertainty. A provider who acknowledges that outcomes vary and can explain the limits of the evidence is generally offering more useful information than one who relies on certainty language such as “guaranteed,” “permanent,” “proven cure,” or “works when nothing else does.”
7.11 Examine how the program describes risk
Risk communication should be proportional rather than frightening or minimizing. A responsible program can explain common acute effects, important serious risks, uncertainties, and the limits of screening without implying that every adverse effect is likely or that screening makes the intervention risk-free. [166]
The details should fit the intervention. For SPRAVATO, current labeling and REMS materials are controlling. For psilocybin, systematic reviews provide information about acute adverse effects while longer-term and rare-event estimates remain less certain. For ibogaine, cardiac risk warrants unusually specific scrutiny. A generic disclaimer copied across modalities is not a substitute for intervention-specific risk communication. [180]
Risk communication also includes what the program does not know. If long-term evidence is limited, say so. If a route is supported mainly by extrapolation, say so. If a foreign program’s legal status has not been independently verified, do not imply that it has. Uncertainty is not a weakness in educational communication; hidden uncertainty is.
7.12 Look for a credible medication-review process
Medication review should be more than a list of prohibited drugs. The interaction literature is heterogeneous, and medication effects can vary by psychedelic, medication class, timing, and context. [119]
A program should not pressure participants to discontinue prescribed medication without appropriate clinical involvement. Research washout requirements should be identified as protocol requirements rather than universal treatment rules. When medication changes are considered in medical care, the relevant prescriber should be involved because discontinuation can itself produce withdrawal, symptom recurrence, or destabilization. [181]
Readers can ask who performs the medication review, whether supplements and nonprescribed substances are included, how uncertainty is handled, and whether the program coordinates with an existing prescriber when needed. A provider who treats every medication as either harmless or absolutely forbidden is simplifying an evidence base that does not support one universal rule.
7.13 Understand the monitoring plan in concrete terms
“Vitals monitored” and “medical monitoring” can mean different things. Readers can ask which measurements are taken, when they are taken, who interprets them, what thresholds or clinical findings prompt action, and what interventions the onsite team can actually provide. [182]
For SPRAVATO, official requirements provide concrete benchmarks. Other pathways may use different monitoring based on the intervention and setting. The purpose of asking is not to demand identical equipment everywhere; it is to understand whether the monitoring plan is intentional and matched to the risk profile. [25]
Emergency planning should likewise be operational. Where is the nearest higher level of care? How is emergency transport activated? Who remains with the participant? What information accompanies a transfer? For ibogaine, the potential for serious arrhythmia makes vague claims of “medical supervision” especially inadequate. [85]
7.14 Evaluate staffing and continuity, not just the lead provider
A program may be built around a highly credentialed founder while day-to-day care is delivered by other staff. Readers should understand who they will actually interact with during screening, preparation, administration, overnight or extended observation if applicable, and follow-up.
Staffing questions include whether the same person follows the participant across stages, how handoffs are documented, what supervision less-experienced staff receive, and what happens if the primary provider is unavailable. [138]
Turnover can also matter. A program that promises a continuing therapeutic relationship should explain how continuity is maintained if staff change. A research study may have protocolized handoffs. A state service center may work with independent facilitators. A medical clinic may use a team model. None is inherently superior, but the structure should match what the program promises.
7.15 Boundaries should include power, not only touch
Touch receives substantial attention in psychedelic ethics because altered states can increase vulnerability, but boundaries extend further. They include sexual and romantic conduct, financial conflicts, dual relationships, spiritual authority, pressure to disclose, recording, use of participant stories, communication outside sessions, and the provider’s influence over how the experience is interpreted. [183]
A participant should be able to disagree with a provider’s interpretation without being told that resistance proves pathology or failure to surrender. Providers should avoid using the authority of the psychedelic experience to impose personal beliefs. These concerns are especially relevant in settings that blend clinical, spiritual, ceremonial, or coaching roles because the boundaries between those roles may otherwise become unclear. [121]
Consent should also remain revocable. Prior agreement to supportive touch does not remove the participant’s continuing right to refuse. Permission to discuss an experience does not imply permission to use it in marketing. Agreement to a program does not eliminate the right to ask questions or seek outside care. [136]
7.16 Review privacy and data use before sharing sensitive
information
Psychedelic programs may collect unusually sensitive information about psychiatric history, trauma, substance use, medications, relationships, spiritual experiences, and session content. Readers should know what is collected, why it is collected, where it is stored, who can access it, and whether recordings or de-identified information may be used for research, training, or marketing. [120]
The applicable privacy framework depends on the setting. A healthcare practice, research institution, and state-regulated service may operate under different rules. A consumer should not assume that every business using clinical language is subject to the same privacy requirements as a conventional healthcare provider. [184]
If a program records sessions, the purpose, storage, access, retention, and consent process should be explicit. Recording can serve legitimate safety, supervision, research, or training purposes in some settings, but it increases the sensitivity of the data and should not be treated as a casual feature.
7.17 Ask how complaints and adverse events are handled
A credible program should be able to explain how participants raise concerns and what happens after a complaint. This may include an internal process, a professional licensing board, a state psychedelic regulator, a research institution, or another jurisdiction-specific authority. [64]
The existence of a complaint process does not prove that misconduct never occurs. Its value is that concerns have a defined route rather than depending entirely on the provider who is the subject of the concern. This is particularly important where altered states, power differentials, or intensive therapeutic relationships can make participants reluctant to challenge a provider. [175]
Adverse-event handling is related but distinct. Programs should know how events are documented, when medical evaluation is sought, and what follow-up occurs. Research has formal protocol requirements. Medical care has clinical and regulatory obligations. State services have their own rules. International programs require local verification. [185]
7.18 Look for coherence between marketing and operations
The final provider-evaluation question is whether the public story matches the actual system. If a program markets itself as medical, are medical roles and responsibilities real and identifiable? If it markets itself as evidence based, do its claims match the studied intervention? If it emphasizes safety, are screening, monitoring, emergency response, and follow-up concrete? If it emphasizes trauma-informed or ethical care, are boundaries, consent, complaints, and staff accountability visible? [186]
Coherence does not require perfection or a particular aesthetic. It requires that claims, credentials, procedures, and accountability point in the same direction. When they do not, the mismatch is useful information for the reader.
8. Cost, insurance, travel, legality, and practical
access
 Evaluating a provider
or program means looking beyond marketing language to credentials, scope,
evidence, safety systems, and accountability.
A polished website, testimonials, professional photography, or the use of words such as “clinical,” “medical,” or “therapeutic” can describe presentation, but they do not establish licensure, legal scope, evidence quality, or safety. A more useful evaluation starts by identifying the exact pathway and then checking whether the provider’s credentials, claims, supervision, safeguards, and follow-up match that pathway. [169]
7.1 Identify what the organization and provider actually are
First determine whether the organization is functioning as a medical practice, a state-regulated service center or healing center, a research site, or an international program. Then identify who performs each role: prescribing, medical screening, psychological assessment, facilitation, psychotherapy, administration-session supervision, emergency response, and follow-up. Specialized psychedelic training may be relevant to preparation and competence, but a course or private certificate is not the same thing as a professional license or legal authority to practice medicine or psychotherapy. [170]
Oregon and Colorado illustrate why this distinction matters. Oregon psilocybin facilitation remains a state-defined role even when a facilitator also holds a separate healthcare license. Colorado distinguishes Facilitators from Clinical Facilitators and ties clinical diagnosis and treatment to the person’s separate qualifying professional license. These rules are jurisdiction-specific, but the broader evaluation principle is transferable: verify the credential that authorizes the actual service being delivered rather than assuming authority from a title. [16]
7.2 Examine the screening process
A serious screening process should be understandable in structure even when the final clinical judgment is individualized. Readers can ask who reviews the intake information, what kinds of concerns trigger additional medical or behavioral-health evaluation, what can lead to referral or nonparticipation, and what professional scope the reviewer has. Research exclusions, product-label contraindications, and state-service screening rules should not be presented as interchangeable. [171]
The quality signal is not simply that a program has a questionnaire. It is whether the screening process is matched to the risks and authority of the specific intervention and whether the program has a clear response when a person falls outside its routine scope. [172]
7.3 Match evidence claims to the exact intervention
Claims such as “FDA approved,” “clinically proven,” “research backed,” or “high success rate” require specificity. Which product or formulation? Which indication? Which study population? Which route and setting? What comparator and follow-up period? An FDA approval for SPRAVATO does not transfer to racemic ketamine or compounded ketamine, and positive psilocybin trials do not establish the effectiveness of every state-regulated service or commercial program. [173]
The same caution applies to emerging evidence. The audited ibogaine cohort supports saying that substantial improvements were reported in a selected observational group, but it does not establish general efficacy or validate the facility where treatment occurred. [47] A responsible provider should be able to distinguish what is established, what is supported but limited, what is investigational, and what remains uncertain.
7.4 Understand supervision and emergency readiness
“Supervised” is not a complete safety description. For SPRAVATO, supervision and monitoring are product-specific regulatory requirements: administration occurs in certified healthcare settings under direct observation, with at least two hours of monitoring and other REMS-linked requirements. Those rules should not be generalized to racemic ketamine, psilocybin services, or other modalities. [34]
For other pathways, readers should identify who remains present, what observations or clinical monitoring occur, what the onsite team is trained and legally authorized to do, and how a medical or psychiatric emergency would be escalated. Oregon requires service-center emergency planning within its own regulated system. Ibogaine raises a different concern because current evidence supports a clinically important QT-prolongation and ventricular-arrhythmia risk; a program’s statement that it “screens carefully” is not proof that this risk has been eliminated. [174]
7.5 Review boundaries, touch, privacy, records, and
accountability before altered states
Professional boundaries should be clear before administration. Ethics guidance supports explicit policies on touch, sexual and romantic boundaries, privacy, recording, observers, and communication. Oregon separately requires prior written consent before supportive touch by a facilitator. These safeguards do not establish that supportive touch is necessary or beneficial; they establish the importance of advance consent and defined limits when participants may be unusually vulnerable. [136]
Safeguarding should not be treated as theoretical. A naturalistic survey has documented reports of sexual misconduct and other adverse experiences in psychedelic contexts, although it cannot establish prevalence in licensed clinical care. That evidence supports asking how a program vets providers, supervises staff, receives complaints, documents concerns, and identifies the regulator or professional body responsible for accountability. [175]
Privacy and record practices also depend on the framework. State-regulated services, healthcare practices, and research programs can operate under different documentation and disclosure rules. Readers should ask what records are created, who can access them, how information may be shared, and what complaint or reporting route applies rather than assuming that every setting operates like a conventional medical practice. [71]
7.6 Look beyond the administration session
Preparation and post-session support can be clinically meaningful parts of some models, but the terminology matters. Integration is described in the literature through diverse frameworks, and current evidence does not establish one standardized integration method as independently responsible for improved outcomes. Integration also should not automatically be called psychotherapy unless the provider’s license, scope, and actual service support that description. [31]
A useful evaluation therefore asks what follow-up is actually provided, who is responsible if symptoms worsen or a medical concern emerges, how referrals are handled, and whether the participant can transition back to ongoing healthcare when the program’s role ends. [140]
7.7 Understand the financial agreement before committing
Financial transparency is part of evaluating a program even though pricing structures vary. Readers should ask for an itemized explanation of professional fees, medication or product costs, facility charges, monitoring, preparation, follow-up, cancellation terms, refunds, and any travel-related expenses that are not included. In Oregon’s regulated system, current rules require specified fee, refund, additional-fee, and product-price information to be provided before money is collected; that is an Oregon-specific protection, not a universal rule for every psychedelic program. [176]
The strongest overall evaluation is not a score or ranking. It is consistency: provider credentials should match the role; evidence claims should match the evidence; screening and supervision should match the risks; boundaries should be established before vulnerability; emergency capability should match foreseeable complications; follow-up should be defined; and accountability should be verifiable.
7.8 Verify licenses and credentials through the issuing authority
A provider biography is a useful starting point, but it is not the final source for a regulated credential. When a service depends on professional licensure or a state psychedelic-service license, readers should verify the credential through the issuing authority where possible. The purpose is not suspicion for its own sake. Licenses can expire, change status, carry restrictions, or apply to a narrower role than a marketing page implies. [16]
Verification should also preserve the distinction between different credentials. A physician license, psychology license, counseling license, facilitator license, clinical-facilitator license, private training certificate, and research affiliation are not interchangeable. A provider may legitimately hold several at once, but each should be understood for the authority it actually conveys. [33]
When a program uses a team model, readers can ask which credential belongs to which team member and who is responsible for each function. The presence of one physician on an advisory board, for example, does not establish that the physician screens every participant or remains responsible during every administration session. “Medical team” should resolve into actual roles.
7.9 Ask who makes the final eligibility decision
Programs often describe screening as collaborative, but the final decision can rest with different people depending on the model. In medical treatment, a qualified clinician may determine whether treatment is appropriate within professional practice and product requirements. In research, investigators apply protocol eligibility. In state-regulated services, facilitators and other professionals operate under jurisdiction-specific rules. [160]
Readers should understand whether the person reviewing medical information has the authority and competence to interpret it. If a facilitator identifies a concern outside their scope, what consultation or referral process follows? If a commercial clinic uses a remote questionnaire, who reviews it and what happens when the answers are ambiguous? If an international program requests an ECG or laboratory result, who interprets it and what standard is used? [177]
The strongest signal is not a long intake form. It is a process that can recognize uncertainty and escalate it appropriately.
7.10 Examine how the program describes benefits
Responsible benefit claims are bounded. They identify the population, condition, intervention, and evidence level rather than promising generalized transformation. [178]
A clinic discussing esketamine should distinguish current approved indications from broader claims about ketamine or psychedelics. A ketamine clinic should distinguish evidence for monitored IV racemic ketamine from claims about compounded or at-home routes. A psilocybin service should not imply that state authorization proves treatment efficacy for depression. An ibogaine program should not convert observational improvement in a selected veteran cohort into a general cure claim. [179]
Testimonials deserve similar caution. Personal stories can communicate lived experience, but they cannot establish average effectiveness, comparative superiority, or safety. Selection is rarely systematic, negative outcomes may be underrepresented, and the person reading the story usually cannot know how similar the storyteller’s clinical circumstances were to their own.
Readers can also notice whether a program discusses nonresponse and uncertainty. A provider who acknowledges that outcomes vary and can explain the limits of the evidence is generally offering more useful information than one who relies on certainty language such as “guaranteed,” “permanent,” “proven cure,” or “works when nothing else does.”
7.11 Examine how the program describes risk
Risk communication should be proportional rather than frightening or minimizing. A responsible program can explain common acute effects, important serious risks, uncertainties, and the limits of screening without implying that every adverse effect is likely or that screening makes the intervention risk-free. [166]
The details should fit the intervention. For SPRAVATO, current labeling and REMS materials are controlling. For psilocybin, systematic reviews provide information about acute adverse effects while longer-term and rare-event estimates remain less certain. For ibogaine, cardiac risk warrants unusually specific scrutiny. A generic disclaimer copied across modalities is not a substitute for intervention-specific risk communication. [180]
Risk communication also includes what the program does not know. If long-term evidence is limited, say so. If a route is supported mainly by extrapolation, say so. If a foreign program’s legal status has not been independently verified, do not imply that it has. Uncertainty is not a weakness in educational communication; hidden uncertainty is.
7.12 Look for a credible medication-review process
Medication review should be more than a list of prohibited drugs. The interaction literature is heterogeneous, and medication effects can vary by psychedelic, medication class, timing, and context. [119]
A program should not pressure participants to discontinue prescribed medication without appropriate clinical involvement. Research washout requirements should be identified as protocol requirements rather than universal treatment rules. When medication changes are considered in medical care, the relevant prescriber should be involved because discontinuation can itself produce withdrawal, symptom recurrence, or destabilization. [181]
Readers can ask who performs the medication review, whether supplements and nonprescribed substances are included, how uncertainty is handled, and whether the program coordinates with an existing prescriber when needed. A provider who treats every medication as either harmless or absolutely forbidden is simplifying an evidence base that does not support one universal rule.
7.13 Understand the monitoring plan in concrete terms
“Vitals monitored” and “medical monitoring” can mean different things. Readers can ask which measurements are taken, when they are taken, who interprets them, what thresholds or clinical findings prompt action, and what interventions the onsite team can actually provide. [182]
For SPRAVATO, official requirements provide concrete benchmarks. Other pathways may use different monitoring based on the intervention and setting. The purpose of asking is not to demand identical equipment everywhere; it is to understand whether the monitoring plan is intentional and matched to the risk profile. [25]
Emergency planning should likewise be operational. Where is the nearest higher level of care? How is emergency transport activated? Who remains with the participant? What information accompanies a transfer? For ibogaine, the potential for serious arrhythmia makes vague claims of “medical supervision” especially inadequate. [85]
7.14 Evaluate staffing and continuity, not just the lead provider
A program may be built around a highly credentialed founder while day-to-day care is delivered by other staff. Readers should understand who they will actually interact with during screening, preparation, administration, overnight or extended observation if applicable, and follow-up.
Staffing questions include whether the same person follows the participant across stages, how handoffs are documented, what supervision less-experienced staff receive, and what happens if the primary provider is unavailable. [138]
Turnover can also matter. A program that promises a continuing therapeutic relationship should explain how continuity is maintained if staff change. A research study may have protocolized handoffs. A state service center may work with independent facilitators. A medical clinic may use a team model. None is inherently superior, but the structure should match what the program promises.
7.15 Boundaries should include power, not only touch
Touch receives substantial attention in psychedelic ethics because altered states can increase vulnerability, but boundaries extend further. They include sexual and romantic conduct, financial conflicts, dual relationships, spiritual authority, pressure to disclose, recording, use of participant stories, communication outside sessions, and the provider’s influence over how the experience is interpreted. [183]
A participant should be able to disagree with a provider’s interpretation without being told that resistance proves pathology or failure to surrender. Providers should avoid using the authority of the psychedelic experience to impose personal beliefs. These concerns are especially relevant in settings that blend clinical, spiritual, ceremonial, or coaching roles because the boundaries between those roles may otherwise become unclear. [121]
Consent should also remain revocable. Prior agreement to supportive touch does not remove the participant’s continuing right to refuse. Permission to discuss an experience does not imply permission to use it in marketing. Agreement to a program does not eliminate the right to ask questions or seek outside care. [136]
7.16 Review privacy and data use before sharing sensitive
information
Psychedelic programs may collect unusually sensitive information about psychiatric history, trauma, substance use, medications, relationships, spiritual experiences, and session content. Readers should know what is collected, why it is collected, where it is stored, who can access it, and whether recordings or de-identified information may be used for research, training, or marketing. [120]
The applicable privacy framework depends on the setting. A healthcare practice, research institution, and state-regulated service may operate under different rules. A consumer should not assume that every business using clinical language is subject to the same privacy requirements as a conventional healthcare provider. [184]
If a program records sessions, the purpose, storage, access, retention, and consent process should be explicit. Recording can serve legitimate safety, supervision, research, or training purposes in some settings, but it increases the sensitivity of the data and should not be treated as a casual feature.
7.17 Ask how complaints and adverse events are handled
A credible program should be able to explain how participants raise concerns and what happens after a complaint. This may include an internal process, a professional licensing board, a state psychedelic regulator, a research institution, or another jurisdiction-specific authority. [64]
The existence of a complaint process does not prove that misconduct never occurs. Its value is that concerns have a defined route rather than depending entirely on the provider who is the subject of the concern. This is particularly important where altered states, power differentials, or intensive therapeutic relationships can make participants reluctant to challenge a provider. [175]
Adverse-event handling is related but distinct. Programs should know how events are documented, when medical evaluation is sought, and what follow-up occurs. Research has formal protocol requirements. Medical care has clinical and regulatory obligations. State services have their own rules. International programs require local verification. [185]
7.18 Look for coherence between marketing and operations
The final provider-evaluation question is whether the public story matches the actual system. If a program markets itself as medical, are medical roles and responsibilities real and identifiable? If it markets itself as evidence based, do its claims match the studied intervention? If it emphasizes safety, are screening, monitoring, emergency response, and follow-up concrete? If it emphasizes trauma-informed or ethical care, are boundaries, consent, complaints, and staff accountability visible? [186]
Coherence does not require perfection or a particular aesthetic. It requires that claims, credentials, procedures, and accountability point in the same direction. When they do not, the mismatch is useful information for the reader.
8. Cost, insurance, travel, legality, and practical
access
 The goal is not to
rank pathways, but to help readers identify which questions matter for the
pathway they are considering.
Compare systems of care rather than substances alone. Five broad pathways are considered without ranking: FDA-regulated medication treatment, off-label medical care, state-regulated adult services, clinical research, and cross-border programs. Evaluate each by its own evidence, authority, provider roles, monitoring, follow-up, and practical access. [11]
Neutral comparison matrix
|
Pathway |
Care goal and preferred setting |
Medical complexity and oversight |
Legal access and evidence frame |
Practical commitment and follow-up |
|
FDA-regulated medication treatment |
FDA-approved product for a labeled indication in a medical setting |
Licensed medical care; product-specific screening and monitoring |
Product-, route-, and indication-specific approval; product-specific requirements |
Repeated visits may apply; verify transportation, coverage, cost, and follow-up |
|
Off-label medical care |
Medical use of an approved drug outside its labeled use |
Licensed medical team; intervention-specific screening and monitoring |
Medical practice, not separate FDA approval; evidence is protocol-specific |
Verify visits, route, monitoring, cost, maintenance, follow-up, and referral |
|
State-regulated adult services |
State-authorized service at licensed service/healing centers |
State-defined facilitator scope, screening, referral, and any separate clinical role |
Jurisdiction-specific access; state authorization is not FDA approval or federal rescheduling |
Verify travel, transportation, fees, insurance, aftercare, and accountability |
|
Clinical research |
Research participation under a defined study protocol |
Study-team oversight with protocol-specific eligibility and monitoring |
Investigational research; trial listing or promising results are not FDA approval |
Verify visits, travel, costs/compensation, withdrawal, follow-up, and post-trial care |
|
Cross-border programs |
Program outside ordinary U.S. pathways; country- and program-specific setting |
Verify screening, monitoring, emergency transfer, provider roles, and recourse |
Marketing does not establish legality, licensure, evidence quality, or medical equivalence |
Verify travel, lodging, total cost, emergency logistics, aftercare, records, and accountability |
This matrix routes comparison; it does not rank pathways or select treatment. [198]
The decision framework is similarly neutral: clarify the care goal, medical or psychiatric complexity, preferred setting and professional relationship, legal access, evidence expectations, time and travel burden, total cost, and desired follow-up. Greater complexity may make professional assessment and emergency capability more important, but this guide does not choose a pathway for the reader. [199]
Evidence expectations differ by pathway: FDA approval, off-label evidence, state-regulated legal access, and investigational research are not interchangeable. The reader—not this article—decides what evidence threshold matters after those distinctions are made visible. [62]
For broader questions about adverse effects, contraindications, difficult experiences, and emergency concerns, readers should also use Psychedelist’s dedicated Safety, Risk and Recovery resources rather than treating this gateway guide as a substitute for individualized clinical evaluation.
A better final question than “Which psychedelic treatment is best?” is: Which pathway am I actually investigating, what evidence and protections apply to it, and what additional information do I need before deciding whether to pursue it?
9.1 Start with the pathway, not the promise
When people compare psychedelic options, the first impulse is often to compare promised outcomes: faster relief, deeper healing, fewer sessions, a more transformative experience, or a more natural approach. Those claims are difficult to evaluate until the underlying pathway is identified. The same promised outcome can be attached to an FDA-approved product, an off-label protocol, a state-regulated service, a research study, or an international program, even though the evidence and accountability behind the promise are very different. [11]
A more reliable sequence is to identify the pathway first and then ask what outcome claims that pathway can actually support. For an approved product, current labeling and trial evidence provide anchors. For off-label care, the reader needs protocol-specific evidence. For a state service, legal authorization and service rules should be distinguished from evidence of treatment efficacy. For research, the study design and published results matter. For cross-border programs, claims require both evidence scrutiny and jurisdiction-specific verification. [200]
This approach does not make the decision for the reader. It prevents a marketing promise from becoming the organizing principle of the decision.
9.2 Separate the care goal from the substance preference
Some readers begin with a preferred substance because they have heard a compelling story about ketamine, psilocybin, or ibogaine. A safer comparison begins with the care goal and the type of professional relationship desired. Is the person seeking treatment of a diagnosed condition within medical care? Exploring a state-regulated adult service? Interested in research participation? Considering a program unavailable through ordinary U.S. pathways? Those questions can narrow the relevant models before the substance becomes the deciding factor. [194]
This distinction is particularly useful when the same substance appears in different contexts. Ketamine may be administered in medical settings using different routes and protocols. Psilocybin may be encountered in clinical research or in state-regulated service systems with different purposes and rules. A reader who asks only “Which substance?” can miss the more consequential question of what system of care surrounds it. [201]
Care goals also influence what follow-up matters. Someone seeking longitudinal psychiatric treatment may reasonably prioritize ongoing symptom assessment and coordination with existing clinicians. Someone entering a time-limited research protocol needs to understand study follow-up and post-trial responsibility. Someone using a state service may prioritize facilitator scope, preparation, administration support, and referral options. None of these priorities establishes that one pathway is universally superior. [129]
9.3 Match medical complexity to actual capability
Medical complexity is not a label a reader should assign to themselves from an online checklist. It is a reason to examine whether the pathway has access to appropriately qualified assessment and whether its setting can manage foreseeable risks. [103]
For an FDA-regulated product, product-specific contraindications, warnings, monitoring, and clinician judgment provide a structured medical framework. For off-label ketamine, the quality of medical assessment and protocol-specific monitoring becomes particularly important because services vary. For state-regulated psilocybin or natural-medicine services, facilitator scope and referral or consultation mechanisms should be understood separately from medical practice. For ibogaine programs, cardiac risk makes the details of cardiovascular assessment, medication review, monitoring, and emergency response unusually consequential. [202]
The practical comparison is therefore not “Which pathway is safest?” in the abstract. It is whether the pathway’s capabilities are proportionate to the individual questions that qualified professionals identify and to the known risks of the intervention.
9.4 Decide what kind of evidence you expect
Readers can reasonably differ in the level and type of evidence they want before pursuing an intervention. The article’s role is to make the evidence category visible rather than impose a single threshold. FDA approval for a defined product and indication represents one evidence-and-regulation threshold. Off-label practice can be supported by meaningful clinical evidence without a separate FDA approval for that use. State authorization can create legal access and consumer protections without proving efficacy for a diagnosis. Clinical research can offer access precisely because efficacy or safety questions remain unresolved. [203]
Evidence expectations should also include uncertainty about durability and generalizability. A reader may care not only whether a trial showed a short-term effect but whether benefit persisted, whether the study population resembles the population of interest, whether the comparator was strong, and whether the intervention being offered matches the studied formulation and support structure. [204]
For ibogaine, the distinction is especially stark: the audited benefit evidence is observational, while the cardiac-risk evidence is sufficiently serious to require prominent attention. A reader who values confirmatory efficacy evidence should understand that imbalance rather than infer equivalence from the fact that all modalities appear in the same guide. [205]
9.5 Compare the whole time commitment
The visible administration session may represent only part of the commitment. Evaluation, preparation, laboratory work when applicable, repeated visits, observation, transportation, integration or follow-up, research assessments, and travel can substantially change the time burden. [160]
Repeated-treatment models make this particularly relevant. Esketamine treatment may involve repeated supervised visits under the approved pathway. Ketamine protocols may involve repeated or maintenance treatment, but the evidence does not establish one universal schedule. Research studies can require visits beyond the intervention itself. State-regulated services may require preparation and administration processes, while international programs can add travel and recovery time. [206]
A pathway that appears convenient based on the drug session alone may be less practical once transportation, observation, time away from work, caregiving, and follow-up are included. Conversely, a pathway with more required structure may provide forms of monitoring or continuity that a reader values. Practical burden is therefore part of informed comparison, not merely an inconvenience.
9.6 Compare total cost without assuming that price signals quality
The most useful cost comparison is comprehensive. Readers should identify evaluation fees, medication or product costs, professional fees, facility charges, monitoring, preparation, follow-up, travel, lodging, laboratory work where applicable, cancellation policies, and refund terms. [207]
Insurance can materially change the comparison but must be verified for the exact service. The fact that a pathway occurs in healthcare does not guarantee coverage, and the fact that a service is state regulated does not create a universal insurance benefit. Research may have study-specific cost or compensation arrangements. International programs may require substantial travel and out-of-pocket spending. [11]
Price should not be treated as an evidence metric. An expensive program may have high operating costs, extensive staffing, luxury amenities, or simply a premium commercial model; none of those factors independently proves efficacy. A less expensive service may be more accessible but should still be evaluated for credentials, scope, safety, and accountability. The decision framework keeps financial burden visible without allowing it to stand in for clinical quality.
9.7 Ask what happens if the expected benefit does not occur
Outcome uncertainty is part of every pathway. Even interventions with randomized evidence do not help every participant, and research findings describe groups rather than guarantee individual results. [208]
A useful provider or program should be able to discuss nonresponse without framing it as personal failure. What reassessment occurs? Is another treatment considered? Does the program continue charging for a fixed series regardless of response? Is there a point at which the provider recommends stopping or seeking another level of care? What happens if symptoms worsen? [209]
This question can reveal whether a program is organized around individualized care or around completion of a predetermined package. It can also expose overpromising. Claims that everyone can heal if they surrender enough, integrate correctly, or complete enough sessions are not supported by the evidence base used in this article.
9.8 Ask what happens if the experience is difficult rather than
beneficial
A difficult acute experience is not automatically a treatment failure, but neither should every distressing or harmful experience be reframed as necessary healing. Ethical care leaves room for both possibilities. [162]
Readers can ask how the team distinguishes expected acute distress from a medical or psychiatric complication, what support is available during the session, how consent and boundaries are maintained, and what follow-up occurs if the participant remains distressed afterward. [210]
The answer should be specific to the pathway. A medical clinic may have clinical escalation procedures. A research study follows protocol-defined safety processes. A state-regulated facilitator operates within a defined scope and may need to refer. An international program should be able to explain its actual onsite capability and transfer plan. [211]
9.9 Verify accountability before relying on trust
Trust is important in any vulnerable care relationship, but accountability should not depend solely on personal trust. Readers can ask who licenses or regulates the provider, where a complaint can be filed, what records exist, what professional or organizational standards apply, and how adverse events or boundary concerns are handled. [212]
In conventional healthcare, professional licensure and healthcare regulation provide familiar accountability routes. State psychedelic programs create their own regulatory mechanisms. Research has institutional and protocol oversight. Cross-border programs require country-specific investigation. A private certification body may offer standards or discipline, but it should not be confused with government licensure. [213]
Accountability is especially important because psychedelic states can involve heightened vulnerability. Advance clarity about touch, privacy, recording, sexual and romantic boundaries, communication, and complaint procedures is a meaningful quality signal. [214]
9.10 Use internal links to go deeper only after identifying the
branch
Once the pathway is clear, a reader can move to a deeper guide without losing the distinctions established here. Someone evaluating ketamine or esketamine can explore formulation, route, evidence, monitoring, and maintenance in detail. Someone considering psilocybin can move into research evidence and the separate Oregon and Colorado frameworks. Someone researching ibogaine can focus on evidence limitations, cardiac risk, program evaluation, and emerging research. The Safety, Risk and Recovery pillar can address adverse effects and emergency concerns that should not be compressed into a gateway comparison.
This routing function is intentional. A long Learning Center article should not force every reader to absorb every downstream technical detail before understanding the landscape. It should give enough information to choose the correct next branch and enough caution to prevent the branch from being mistaken for a recommendation.
10. Conclusion and next steps
 Responsible
psychedelic care involves more than access to a substance; it includes
screening, support, follow-up, and accountability.
Psychedelic-related care is not one treatment category. FDA-approved esketamine, off-label racemic ketamine, state-regulated psilocybin or natural-medicine services, investigational clinical trials, and international programs can all appear in the same public conversation while operating under very different evidence and regulatory frameworks. [11]
The most important distinction is often between an appealing intervention and a responsible system of care. A responsible system begins before administration with accurate description of what is offered, appropriate screening, informed consent, provider scope, preparation, supervision, boundaries, and emergency planning. It continues afterward through defined follow-up, referral, and accountability. Regulation alone does not guarantee quality, and emerging evidence should neither be promoted as established treatment nor dismissed simply because it is still developing. [167]
This guide is intended to help readers identify the Publication currentness note: the evidence synthesis retains a September 1, 2026 research cutoff. Publication-sensitive regulatory material received an additional currentness check on September 11, 2026. Oregon’s 2026 psilocybin rulemaking remains in the proposed-rule/public-comment stage and is not treated here as operative law. Final publication should still reopen controlling product labeling, REMS, federal scheduling, and state-rule sources immediately before release.
pathway they are considering and evaluate the evidence, authority, safeguards, practical access, and unresolved questions that come with it. It does not select a treatment or provide individualized medical, psychiatric, or legal advice. Eligibility, medication decisions, contraindications, and treatment choices should be discussed with appropriately qualified professionals, and time-sensitive legal or regulatory information should be rechecked in the relevant jurisdiction before it is relied upon. [215]
References
Each bracketed number in the article points to one numbered reference note below. Each note identifies the complete source record or records supporting that passage. Full publication details and one stable clickable link per item appear in the Sources section.
[1] S7, DailyMed, KETALAR prescribing information (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[2] S7, DailyMed, KETALAR prescribing information (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S18, ClinicalTrials.gov, NCT03775200; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[3] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S3, Reiff et al., Psychedelics and Psychedelic-Assisted Psychotherapy (2020); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S31, Guo et al., ketamine and esketamine safety meta-analysis (2025); S49, Brunt, ibogaine cardiovascular complications (2026).
[4] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S46, 21 CFR 1308.11(d)(29)-(30), psilocybin and psilocyn; S47, 21 CFR 1308.11(d)(21), ibogaine; S48, Cherian et al., magnesium-ibogaine observational study (2024); S49, Brunt, ibogaine cardiovascular complications (2026).
[5] S3, Reiff et al., Psychedelics and Psychedelic-Assisted Psychotherapy (2020); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[6] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023); S12, DailyMed, SPRAVATO prescribing information (2026); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S45, DEA, Controlled Substances Act; S46, 21 CFR 1308.11(d)(29)-(30), psilocybin and psilocyn.
[7] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1; S32, Hinkle et al., classic-psychedelic adverse-events meta-analysis (2024).
[8] S7, DailyMed, KETALAR prescribing information (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019); S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021); S47, 21 CFR 1308.11(d)(21), ibogaine; S48, Cherian et al., magnesium-ibogaine observational study (2024); S49, Brunt, ibogaine cardiovascular complications (2026).
[9] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1.
[10] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1.
[11] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[12] S7, DailyMed, KETALAR prescribing information (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[13] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023); S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026).
[14] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S24, Oregon Health Authority, licensed-facilitator guidance (2026); S25, Oregon Health Authority, licensed-service-center guidance (2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S27, Colorado General Assembly, SB23-290; S28, Colorado General Assembly, SB24-198; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1; S45, DEA, Controlled Substances Act; S46, 21 CFR 1308.11(d)(29)-(30), psilocybin and psilocyn.
[15] S16, NIH, Clinical Research Trials and You; S18, ClinicalTrials.gov, NCT03775200.
[16] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S24, Oregon Health Authority, licensed-facilitator guidance (2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[17] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S52, Oregon Health Authority, 2026 psilocybin rulemaking.
[18] S39, Phelps, psychedelic-therapist competencies (2017); S40, McGuire et al., ethics and policy consensus statement (2024).
[19] S3, Reiff et al., Psychedelics and Psychedelic-Assisted Psychotherapy (2020); S7, DailyMed, KETALAR prescribing information (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[20] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S45, DEA, Controlled Substances Act.
[21] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S45, DEA, Controlled Substances Act.
[22] S12, DailyMed, SPRAVATO prescribing information (2026); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S45, DEA, Controlled Substances Act; S46, 21 CFR 1308.11(d)(29)-(30), psilocybin and psilocyn; S47, 21 CFR 1308.11(d)(21), ibogaine.
[23] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S24, Oregon Health Authority, licensed-facilitator guidance (2026).
[24] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S40, McGuire et al., ethics and policy consensus statement (2024).
[25] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[26] S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021); S37, Cavarra et al., psychological interventions systematic review (2022).
[27] S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021).
[28] S37, Cavarra et al., psychological interventions systematic review (2022); S38, Thal et al., integration-session frameworks review (2024); S39, Phelps, psychedelic-therapist competencies (2017).
[29] S38, Thal et al., integration-session frameworks review (2024).
[30] S38, Thal et al., integration-session frameworks review (2024); S40, McGuire et al., ethics and policy consensus statement (2024).
[31] S37, Cavarra et al., psychological interventions systematic review (2022); S38, Thal et al., integration-session frameworks review (2024).
[32] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S39, Phelps, psychedelic-therapist competencies (2017).
[33] S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S39, Phelps, psychedelic-therapist competencies (2017).
[34] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026).
[35] S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019); S31, Guo et al., ketamine and esketamine safety meta-analysis (2025).
[36] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023).
[37] S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S11, Phillips et al., repeated and maintenance ketamine trial (2019).
[38] S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S31, Guo et al., ketamine and esketamine safety meta-analysis (2025).
[39] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S46, 21 CFR 1308.11(d)(29)-(30), psilocybin and psilocyn.
[40] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S24, Oregon Health Authority, licensed-facilitator guidance (2026).
[41] S23, Oregon Administrative Rules, Chapter 333, Division 333; S24, Oregon Health Authority, licensed-facilitator guidance (2026); S25, Oregon Health Authority, licensed-service-center guidance (2026).
[42] S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S27, Colorado General Assembly, SB23-290; S28, Colorado General Assembly, SB24-198; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1.
[43] S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1.
[44] S30, Colorado General Assembly, HB26-1325; S47, 21 CFR 1308.11(d)(21), ibogaine.
[45] S16, NIH, Clinical Research Trials and You.
[46] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S18, ClinicalTrials.gov, NCT03775200.
[47] S48, Cherian et al., magnesium-ibogaine observational study (2024).
[48] S47, 21 CFR 1308.11(d)(21), ibogaine; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[49] S48, Cherian et al., magnesium-ibogaine observational study (2024); S49, Brunt, ibogaine cardiovascular complications (2026); S50, Rubi et al., ibogaine cardiomyocyte study (2017); S51, Henstra et al., ibogaine toxicokinetics case report (2017).
[50] S3, Reiff et al., Psychedelics and Psychedelic-Assisted Psychotherapy (2020); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S31, Guo et al., ketamine and esketamine safety meta-analysis (2025); S49, Brunt, ibogaine cardiovascular complications (2026).
[51] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S18, ClinicalTrials.gov, NCT03775200; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[52] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S37, Cavarra et al., psychological interventions systematic review (2022).
[53] S12, DailyMed, SPRAVATO prescribing information (2026); S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019).
[54] S7, DailyMed, KETALAR prescribing information (2026); S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S11, Phillips et al., repeated and maintenance ketamine trial (2019).
[55] S8, FDA, compounded ketamine risk alert (2023).
[56] S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021).
[57] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1.
[58] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[59] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[60] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S16, NIH, Clinical Research Trials and You.
[61] S40, McGuire et al., ethics and policy consensus statement (2024); S48, Cherian et al., magnesium-ibogaine observational study (2024).
[62] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[63] S8, FDA, compounded ketamine risk alert (2023); S12, DailyMed, SPRAVATO prescribing information (2026); S19, Raison et al., psilocybin for major depressive disorder (2023); S40, McGuire et al., ethics and policy consensus statement (2024).
[64] S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[65] S23, Oregon Administrative Rules, Chapter 333, Division 333; S24, Oregon Health Authority, licensed-facilitator guidance (2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[66] S12, DailyMed, SPRAVATO prescribing information (2026); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1.
[67] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[68] S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[69] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S18, ClinicalTrials.gov, NCT03775200; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[70] S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[71] S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1.
[72] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[73] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S3, Reiff et al., Psychedelics and Psychedelic-Assisted Psychotherapy (2020); S7, DailyMed, KETALAR prescribing information (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S19, Raison et al., psilocybin for major depressive disorder (2023); S48, Cherian et al., magnesium-ibogaine observational study (2024).
[74] S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019).
[75] S12, DailyMed, SPRAVATO prescribing information (2026); S15, Daly et al., esketamine relapse-prevention trial (2019).
[76] S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S11, Phillips et al., repeated and maintenance ketamine trial (2019).
[77] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S31, Guo et al., ketamine and esketamine safety meta-analysis (2025).
[78] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023); S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S31, Guo et al., ketamine and esketamine safety meta-analysis (2025).
[79] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S46, 21 CFR 1308.11(d)(29)-(30), psilocybin and psilocyn.
[80] S19, Raison et al., psilocybin for major depressive disorder (2023).
[81] S20, Davis et al., psilocybin-assisted therapy trial (2021).
[82] S21, Carhart-Harris et al., psilocybin versus escitalopram (2021).
[83] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S4, Muthukumaraswamy, Forsyth, and Lumley, blinding and expectancy confounds (2021); S5, Aday et al., methodological rigor in psychedelic trials (2022); S6, Hovmand et al., risk of bias systematic review (2023).
[84] S32, Hinkle et al., classic-psychedelic adverse-events meta-analysis (2024); S33, Yerubandi et al., psilocybin acute adverse-effects meta-analysis (2024); S34, Breeksema et al., adverse events in psychedelic and MDMA treatment (2022).
[85] S49, Brunt, ibogaine cardiovascular complications (2026); S50, Rubi et al., ibogaine cardiomyocyte study (2017); S51, Henstra et al., ibogaine toxicokinetics case report (2017).
[86] S11, Phillips et al., repeated and maintenance ketamine trial (2019); S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019); S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021); S48, Cherian et al., magnesium-ibogaine observational study (2024); S49, Brunt, ibogaine cardiovascular complications (2026).
[87] S18, ClinicalTrials.gov, NCT03775200.
[88] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S4, Muthukumaraswamy, Forsyth, and Lumley, blinding and expectancy confounds (2021); S5, Aday et al., methodological rigor in psychedelic trials (2022); S6, Hovmand et al., risk of bias systematic review (2023); S16, NIH, Clinical Research Trials and You; S18, ClinicalTrials.gov, NCT03775200.
[89] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019); S31, Guo et al., ketamine and esketamine safety meta-analysis (2025).
[90] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023); S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S11, Phillips et al., repeated and maintenance ketamine trial (2019).
[91] S4, Muthukumaraswamy, Forsyth, and Lumley, blinding and expectancy confounds (2021); S6, Hovmand et al., risk of bias systematic review (2023); S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021); S32, Hinkle et al., classic-psychedelic adverse-events meta-analysis (2024); S33, Yerubandi et al., psilocybin acute adverse-effects meta-analysis (2024).
[92] S47, 21 CFR 1308.11(d)(21), ibogaine; S48, Cherian et al., magnesium-ibogaine observational study (2024); S49, Brunt, ibogaine cardiovascular complications (2026); S50, Rubi et al., ibogaine cardiomyocyte study (2017); S51, Henstra et al., ibogaine toxicokinetics case report (2017).
[93] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S31, Guo et al., ketamine and esketamine safety meta-analysis (2025); S49, Brunt, ibogaine cardiovascular complications (2026).
[94] S4, Muthukumaraswamy, Forsyth, and Lumley, blinding and expectancy confounds (2021); S5, Aday et al., methodological rigor in psychedelic trials (2022); S6, Hovmand et al., risk of bias systematic review (2023).
[95] S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021); S37, Cavarra et al., psychological interventions systematic review (2022); S38, Thal et al., integration-session frameworks review (2024).
[96] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S19, Raison et al., psilocybin for major depressive disorder (2023); S48, Cherian et al., magnesium-ibogaine observational study (2024).
[97] S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019); S19, Raison et al., psilocybin for major depressive disorder (2023).
[98] S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S11, Phillips et al., repeated and maintenance ketamine trial (2019); S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019); S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021).
[99] S4, Muthukumaraswamy, Forsyth, and Lumley, blinding and expectancy confounds (2021); S5, Aday et al., methodological rigor in psychedelic trials (2022).
[100] S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S30, Colorado General Assembly, HB26-1325; S46, 21 CFR 1308.11(d)(29)-(30), psilocybin and psilocyn; S47, 21 CFR 1308.11(d)(21), ibogaine; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[101] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S32, Hinkle et al., classic-psychedelic adverse-events meta-analysis (2024); S33, Yerubandi et al., psilocybin acute adverse-effects meta-analysis (2024); S34, Breeksema et al., adverse events in psychedelic and MDMA treatment (2022).
[102] S12, DailyMed, SPRAVATO prescribing information (2026); S31, Guo et al., ketamine and esketamine safety meta-analysis (2025); S32, Hinkle et al., classic-psychedelic adverse-events meta-analysis (2024); S33, Yerubandi et al., psilocybin acute adverse-effects meta-analysis (2024); S34, Breeksema et al., adverse events in psychedelic and MDMA treatment (2022); S49, Brunt, ibogaine cardiovascular complications (2026); S50, Rubi et al., ibogaine cardiomyocyte study (2017); S51, Henstra et al., ibogaine toxicokinetics case report (2017).
[103] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S49, Brunt, ibogaine cardiovascular complications (2026).
[104] S7, DailyMed, KETALAR prescribing information (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S19, Raison et al., psilocybin for major depressive disorder (2023); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S48, Cherian et al., magnesium-ibogaine observational study (2024); S49, Brunt, ibogaine cardiovascular complications (2026).
[105] S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S37, Cavarra et al., psychological interventions systematic review (2022).
[106] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023); S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021).
[107] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023); S12, DailyMed, SPRAVATO prescribing information (2026).
[108] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023); S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S11, Phillips et al., repeated and maintenance ketamine trial (2019); S12, DailyMed, SPRAVATO prescribing information (2026).
[109] S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S11, Phillips et al., repeated and maintenance ketamine trial (2019); S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019).
[110] S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S15, Daly et al., esketamine relapse-prevention trial (2019).
[111] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S18, ClinicalTrials.gov, NCT03775200; S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021).
[112] S18, ClinicalTrials.gov, NCT03775200; S19, Raison et al., psilocybin for major depressive disorder (2023).
[113] S12, DailyMed, SPRAVATO prescribing information (2026); S31, Guo et al., ketamine and esketamine safety meta-analysis (2025).
[114] S49, Brunt, ibogaine cardiovascular complications (2026).
[115] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S27, Colorado General Assembly, SB23-290; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[116] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S27, Colorado General Assembly, SB23-290.
[117] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[118] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S18, ClinicalTrials.gov, NCT03775200; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[119] S35, Halman et al., classic-psychedelic drug interactions (2024); S36, Sarparast et al., psychiatric-medication interactions with MDMA or psilocybin (2022).
[120] S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[121] S40, McGuire et al., ethics and policy consensus statement (2024).
[122] S23, Oregon Administrative Rules, Chapter 333, Division 333; S27, Colorado General Assembly, SB23-290; S37, Cavarra et al., psychological interventions systematic review (2022).
[123] S24, Oregon Health Authority, licensed-facilitator guidance (2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S37, Cavarra et al., psychological interventions systematic review (2022); S38, Thal et al., integration-session frameworks review (2024).
[124] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S27, Colorado General Assembly, SB23-290; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1.
[125] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S16, NIH, Clinical Research Trials and You; S18, ClinicalTrials.gov, NCT03775200.
[126] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[127] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S24, Oregon Health Authority, licensed-facilitator guidance (2026).
[128] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S24, Oregon Health Authority, licensed-facilitator guidance (2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[129] S2, Destoop et al., EPA policy paper (2025); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[130] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S24, Oregon Health Authority, licensed-facilitator guidance (2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[131] S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S25, Oregon Health Authority, licensed-service-center guidance (2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1.
[132] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[133] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[134] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[135] S4, Muthukumaraswamy, Forsyth, and Lumley, blinding and expectancy confounds (2021); S5, Aday et al., methodological rigor in psychedelic trials (2022); S40, McGuire et al., ethics and policy consensus statement (2024).
[136] S23, Oregon Administrative Rules, Chapter 333, Division 333; S40, McGuire et al., ethics and policy consensus statement (2024); S41, McHerron et al., therapeutic touch qualitative study (2025).
[137] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[138] S2, Destoop et al., EPA policy paper (2025); S39, Phelps, psychedelic-therapist competencies (2017); S40, McGuire et al., ethics and policy consensus statement (2024).
[139] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S40, McGuire et al., ethics and policy consensus statement (2024).
[140] S2, Destoop et al., EPA policy paper (2025); S40, McGuire et al., ethics and policy consensus statement (2024).
[141] S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[142] S37, Cavarra et al., psychological interventions systematic review (2022); S38, Thal et al., integration-session frameworks review (2024); S40, McGuire et al., ethics and policy consensus statement (2024).
[143] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[144] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S49, Brunt, ibogaine cardiovascular complications (2026).
[145] S2, Destoop et al., EPA policy paper (2025); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[146] S2, Destoop et al., EPA policy paper (2025); S16, NIH, Clinical Research Trials and You; S18, ClinicalTrials.gov, NCT03775200; S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021).
[147] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026).
[148] S12, DailyMed, SPRAVATO prescribing information (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333.
[149] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S18, ClinicalTrials.gov, NCT03775200; S23, Oregon Administrative Rules, Chapter 333, Division 333.
[150] S36, Sarparast et al., psychiatric-medication interactions with MDMA or psilocybin (2022); S18, ClinicalTrials.gov, NCT03775200.
[151] S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S35, Halman et al., classic-psychedelic drug interactions (2024); S36, Sarparast et al., psychiatric-medication interactions with MDMA or psilocybin (2022).
[152] S16, NIH, Clinical Research Trials and You; S40, McGuire et al., ethics and policy consensus statement (2024).
[153] S23, Oregon Administrative Rules, Chapter 333, Division 333; S40, McGuire et al., ethics and policy consensus statement (2024).
[154] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S24, Oregon Health Authority, licensed-facilitator guidance (2026).
[155] S2, Destoop et al., EPA policy paper (2025); S49, Brunt, ibogaine cardiovascular complications (2026); S50, Rubi et al., ibogaine cardiomyocyte study (2017); S51, Henstra et al., ibogaine toxicokinetics case report (2017).
[156] S2, Destoop et al., EPA policy paper (2025); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[157] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S35, Halman et al., classic-psychedelic drug interactions (2024); S36, Sarparast et al., psychiatric-medication interactions with MDMA or psilocybin (2022); S49, Brunt, ibogaine cardiovascular complications (2026).
[158] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S2, Destoop et al., EPA policy paper (2025); S16, NIH, Clinical Research Trials and You.
[159] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[160] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[161] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S2, Destoop et al., EPA policy paper (2025); S40, McGuire et al., ethics and policy consensus statement (2024).
[162] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S40, McGuire et al., ethics and policy consensus statement (2024).
[163] S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S39, Phelps, psychedelic-therapist competencies (2017); S40, McGuire et al., ethics and policy consensus statement (2024).
[164] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S16, NIH, Clinical Research Trials and You; S32, Hinkle et al., classic-psychedelic adverse-events meta-analysis (2024); S34, Breeksema et al., adverse events in psychedelic and MDMA treatment (2022).
[165] S2, Destoop et al., EPA policy paper (2025); S16, NIH, Clinical Research Trials and You; S40, McGuire et al., ethics and policy consensus statement (2024).
[166] S12, DailyMed, SPRAVATO prescribing information (2026); S31, Guo et al., ketamine and esketamine safety meta-analysis (2025); S32, Hinkle et al., classic-psychedelic adverse-events meta-analysis (2024); S33, Yerubandi et al., psilocybin acute adverse-effects meta-analysis (2024); S34, Breeksema et al., adverse events in psychedelic and MDMA treatment (2022); S49, Brunt, ibogaine cardiovascular complications (2026).
[167] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024); S49, Brunt, ibogaine cardiovascular complications (2026).
[168] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[169] S12, DailyMed, SPRAVATO prescribing information (2026); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S39, Phelps, psychedelic-therapist competencies (2017); S40, McGuire et al., ethics and policy consensus statement (2024).
[170] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S39, Phelps, psychedelic-therapist competencies (2017); S40, McGuire et al., ethics and policy consensus statement (2024).
[171] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[172] S2, Destoop et al., EPA policy paper (2025); S49, Brunt, ibogaine cardiovascular complications (2026).
[173] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023); S12, DailyMed, SPRAVATO prescribing information (2026); S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021).
[174] S23, Oregon Administrative Rules, Chapter 333, Division 333; S49, Brunt, ibogaine cardiovascular complications (2026); S50, Rubi et al., ibogaine cardiomyocyte study (2017); S51, Henstra et al., ibogaine toxicokinetics case report (2017).
[175] S40, McGuire et al., ethics and policy consensus statement (2024); S42, Kruger et al., therapist misconduct and adverse experiences (2025).
[176] S23, Oregon Administrative Rules, Chapter 333, Division 333.
[177] S2, Destoop et al., EPA policy paper (2025); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S49, Brunt, ibogaine cardiovascular complications (2026).
[178] S4, Muthukumaraswamy, Forsyth, and Lumley, blinding and expectancy confounds (2021); S5, Aday et al., methodological rigor in psychedelic trials (2022); S6, Hovmand et al., risk of bias systematic review (2023); S19, Raison et al., psilocybin for major depressive disorder (2023).
[179] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023); S12, DailyMed, SPRAVATO prescribing information (2026); S19, Raison et al., psilocybin for major depressive disorder (2023); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S48, Cherian et al., magnesium-ibogaine observational study (2024).
[180] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S32, Hinkle et al., classic-psychedelic adverse-events meta-analysis (2024); S33, Yerubandi et al., psilocybin acute adverse-effects meta-analysis (2024); S34, Breeksema et al., adverse events in psychedelic and MDMA treatment (2022); S49, Brunt, ibogaine cardiovascular complications (2026); S50, Rubi et al., ibogaine cardiomyocyte study (2017); S51, Henstra et al., ibogaine toxicokinetics case report (2017).
[181] S18, ClinicalTrials.gov, NCT03775200; S35, Halman et al., classic-psychedelic drug interactions (2024); S36, Sarparast et al., psychiatric-medication interactions with MDMA or psilocybin (2022).
[182] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S49, Brunt, ibogaine cardiovascular complications (2026).
[183] S40, McGuire et al., ethics and policy consensus statement (2024); S41, McHerron et al., therapeutic touch qualitative study (2025); S42, Kruger et al., therapist misconduct and adverse experiences (2025).
[184] S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[185] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[186] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S39, Phelps, psychedelic-therapist competencies (2017); S40, McGuire et al., ethics and policy consensus statement (2024).
[187] S43, Hughes and Garcia-Romeu, ethnoracial inclusion systematic review (2024); S44, Grossman et al., income and education reporting systematic review (2025).
[188] S17, Ross and Soeteman, esketamine cost-effectiveness (2020).
[189] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[190] S23, Oregon Administrative Rules, Chapter 333, Division 333; S43, Hughes and Garcia-Romeu, ethnoracial inclusion systematic review (2024); S44, Grossman et al., income and education reporting systematic review (2025).
[191] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S45, DEA, Controlled Substances Act; S46, 21 CFR 1308.11(d)(29)-(30), psilocybin and psilocyn; S47, 21 CFR 1308.11(d)(21), ibogaine.
[192] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S40, McGuire et al., ethics and policy consensus statement (2024).
[193] S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024); S48, Cherian et al., magnesium-ibogaine observational study (2024).
[194] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[195] S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1.
[196] S2, Destoop et al., EPA policy paper (2025); S40, McGuire et al., ethics and policy consensus statement (2024); S48, Cherian et al., magnesium-ibogaine observational study (2024).
[197] S12, DailyMed, SPRAVATO prescribing information (2026); S13, SPRAVATO REMS Program Overview (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333.
[198] S7, DailyMed, KETALAR prescribing information (2026); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1; S48, Cherian et al., magnesium-ibogaine observational study (2024); S49, Brunt, ibogaine cardiovascular complications (2026).
[199] S2, Destoop et al., EPA policy paper (2025); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S40, McGuire et al., ethics and policy consensus statement (2024); S44, Grossman et al., income and education reporting systematic review (2025).
[200] S7, DailyMed, KETALAR prescribing information (2026); S8, FDA, compounded ketamine risk alert (2023); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[201] S7, DailyMed, KETALAR prescribing information (2026); S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S19, Raison et al., psilocybin for major depressive disorder (2023); S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[202] S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S12, DailyMed, SPRAVATO prescribing information (2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S49, Brunt, ibogaine cardiovascular complications (2026); S50, Rubi et al., ibogaine cardiomyocyte study (2017); S51, Henstra et al., ibogaine toxicokinetics case report (2017).
[203] S7, DailyMed, KETALAR prescribing information (2026); S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1.
[204] S4, Muthukumaraswamy, Forsyth, and Lumley, blinding and expectancy confounds (2021); S5, Aday et al., methodological rigor in psychedelic trials (2022); S6, Hovmand et al., risk of bias systematic review (2023); S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019); S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021).
[205] S48, Cherian et al., magnesium-ibogaine observational study (2024); S49, Brunt, ibogaine cardiovascular complications (2026).
[206] S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[207] S17, Ross and Soeteman, esketamine cost-effectiveness (2020); S23, Oregon Administrative Rules, Chapter 333, Division 333.
[208] S14, Popova et al., esketamine randomized trial (2019); S15, Daly et al., esketamine relapse-prevention trial (2019); S19, Raison et al., psilocybin for major depressive disorder (2023); S20, Davis et al., psilocybin-assisted therapy trial (2021); S21, Carhart-Harris et al., psilocybin versus escitalopram (2021).
[209] S2, Destoop et al., EPA policy paper (2025); S9, Swainson et al., CANMAT racemic ketamine recommendations (2021); S10, McIntyre et al., ketamine and esketamine expert opinion (2021); S40, McGuire et al., ethics and policy consensus statement (2024).
[210] S1, FDA, Psychedelic Drugs: Considerations for Clinical Investigations (2026); S2, Destoop et al., EPA policy paper (2025); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[211] S12, DailyMed, SPRAVATO prescribing information (2026); S16, NIH, Clinical Research Trials and You; S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S48, Cherian et al., magnesium-ibogaine observational study (2024).
[212] S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S29, Colorado Department of Revenue, Natural Medicine Rules, 1 CCR 213-1; S40, McGuire et al., ethics and policy consensus statement (2024).
[213] S16, NIH, Clinical Research Trials and You; S22, Oregon Revised Statutes, Chapter 475A (2025-2026); S23, Oregon Administrative Rules, Chapter 333, Division 333; S26, Colorado DORA, Natural Medicine Licensure Rules, 4 CCR 755-1; S39, Phelps, psychedelic-therapist competencies (2017).
[214] S23, Oregon Administrative Rules, Chapter 333, Division 333; S40, McGuire et al., ethics and policy consensus statement (2024); S41, McHerron et al., therapeutic touch qualitative study (2025); S42, Kruger et al., therapist misconduct and adverse experiences (2025).
[215] S12, DailyMed, SPRAVATO prescribing information (2026); S35, Halman et al., classic-psychedelic drug interactions (2024); S36, Sarparast et al., psychiatric-medication interactions with MDMA or psilocybin (2022); S49, Brunt, ibogaine cardiovascular complications (2026); S52, Oregon Health Authority, 2026 psilocybin rulemaking.
Sources
These 52 full source records reproduce the article's original bibliography under its corrected heading. The S-number provides an unambiguous crosswalk from the numbered References above; S-numbers are not the article's inline annotations.
[S1] U.S. Food and Drug Administration. Psychedelic Drugs: Considerations for Clinical Investigations: Guidance for Industry. Final Guidance. July 2026. Accessed September 2, 2026. https://www.fda.gov/regulatory-information/search-fda-guidance-documents/psychedelic-drugs-considerations-clinical-investigations
[S2] Destoop M, Mohr P, Butlen F, Keri P, Samochowiec J, De Picker L, Fiorillo A, Kuypers KPC, Dom G. Use of psychedelic treatments in psychiatric clinical practice: an EPA policy paper. European Psychiatry. 2025;68(1):e3. doi:10.1192/j.eurpsy.2024.1806. https://www.cambridge.org/core/journals/european-psychiatry/article/use-of-psychedelic-treatments-in-psychiatric-clinical-practice-an-epa-policy-paper/340B7D729CF69904BB989B24FA0D60F7
[S3] Reiff CM, Richman EE, Nemeroff CB, et al. Psychedelics and Psychedelic-Assisted Psychotherapy. American Journal of Psychiatry. 2020;177(5):391-410. doi:10.1176/appi.ajp.2019.19010035. https://doi.org/10.1176/appi.ajp.2019.19010035
[S4] Muthukumaraswamy SD, Forsyth A, Lumley T. Blinding and Expectancy Confounds in Psychedelic Randomized Controlled Trials. Expert Review of Clinical Pharmacology. 2021;14(9):1133-1152. doi:10.1080/17512433.2021.1933434. https://doi.org/10.1080/17512433.2021.1933434
[S5] Aday JS, Heifets BD, Pratscher SD, Bradley E, Rosen R, Woolley JD. Great Expectations: recommendations for improving the methodological rigor of psychedelic clinical trials. Psychopharmacology (Berl). 2022;239(6):1989-2010. doi:10.1007/s00213-022-06123-7. https://doi.org/10.1007/s00213-022-06123-7
[S6] Hovmand OR, Poulsen ED, Arnfred S, Storebo OJ. Risk of Bias in Randomized Clinical Trials on Psychedelic Medicine: A Systematic Review. Journal of Psychopharmacology. 2023;37(7):649-659. doi:10.1177/02698811231180276. https://doi.org/10.1177/02698811231180276
[S7] National Library of Medicine / FDA labeling. KETALAR (ketamine hydrochloride) injection. DailyMed. Updated March 27, 2026. Accessed September 2, 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=14e8f864-8b8a-4e7e-8439-e510d3107063
[S8] U.S. Food and Drug Administration. FDA Warns Patients and Health Care Providers About Potential Risks Associated With Compounded Ketamine Products, Including Oral Formulations, for the Treatment of Psychiatric Disorders. October 10, 2023. Accessed September 2, 2026. https://www.fda.gov/drugs/human-drug-compounding/compounding-risk-alerts
[S9] Swainson J, McGirr A, Blier P, et al. The CANMAT Task Force Recommendations for the Use of Racemic Ketamine in Adults With Major Depressive Disorder. Canadian Journal of Psychiatry. 2021;66(2):113-125. doi:10.1177/0706743720970860. Correction: 2021;66(12):1102. doi:10.1177/07067437211035276. https://doi.org/10.1177/0706743720970860
[S10] McIntyre RS, Rosenblat JD, Nemeroff CB, et al. Synthesizing the Evidence for Ketamine and Esketamine in Treatment-Resistant Depression: An International Expert Opinion on the Available Evidence and Implementation. American Journal of Psychiatry. 2021;178(5):383-399. doi:10.1176/appi.ajp.2020.20081251. https://doi.org/10.1176/appi.ajp.2020.20081251
[S11] Phillips JL, Norris S, Talbot J, et al. Single, Repeated, and Maintenance Ketamine Infusions for Treatment-Resistant Depression: A Randomized Controlled Trial. American Journal of Psychiatry. 2019;176(5):401-409. doi:10.1176/appi.ajp.2018.18070834. https://doi.org/10.1176/appi.ajp.2018.18070834
[S12] National Library of Medicine / FDA labeling. SPRAVATO (esketamine) nasal spray - Prescribing Information. DailyMed SPL version 19 effective July 29, 2026; PI revised March 2026. Accessed September 2, 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d81a6a79-a74a-44b7-822c-0dfa3036eaed
[S13] SPRAVATO REMS Program Overview. Current FDA-required REMS program materials; program overview audited August 30, 2026. Accessed September 2, 2026. https://www.spravatorems.com/
[S14] Popova V, Daly EJ, Trivedi M, et al. Efficacy and Safety of Flexibly Dosed Esketamine Nasal Spray Combined With a Newly Initiated Oral Antidepressant in Treatment-Resistant Depression: A Randomized Double-Blind Active-Controlled Study. American Journal of Psychiatry. 2019;176(6):428-438. doi:10.1176/appi.ajp.2019.19020172. https://doi.org/10.1176/appi.ajp.2019.19020172
[S15] Daly EJ, Trivedi MH, Janik A, et al. Efficacy of Esketamine Nasal Spray Plus Oral Antidepressant Treatment for Relapse Prevention in Patients With Treatment-Resistant Depression: A Randomized Clinical Trial. JAMA Psychiatry. 2019;76(9):893-903. doi:10.1001/jamapsychiatry.2019.1189. https://doi.org/10.1001/jamapsychiatry.2019.1189
[S16] National Institutes of Health. Clinical Research Trials and You: The Basics. Current NIH participant-education page. Accessed September 2, 2026. https://www.nih.gov/health-information/nih-clinical-research-trials-you/basics
[S17] Ross EL, Soeteman DI. Cost-effectiveness of esketamine nasal spray for patients with treatment-resistant depression in the United States. Psychiatric Services. 2020;71(10):988-997. doi:10.1176/appi.ps.201900625. https://doi.org/10.1176/appi.ps.201900625
[S18] ClinicalTrials.gov. NCT03775200. The Safety and Efficacy of Psilocybin in Participants With Treatment Resistant Depression (P-TRD / COMP001). Sponsor: COMPASS Pathways. Accessed September 2, 2026. https://clinicaltrials.gov/study/NCT03775200
[S19] Raison CL, Sanacora G, Woolley J, et al. Single-Dose Psilocybin Treatment for Major Depressive Disorder: A Randomized Clinical Trial. JAMA. 2023;330(9):843-853. doi:10.1001/jama.2023.14530. Corrected January 26, 2024. https://doi.org/10.1001/jama.2023.14530
[S20] Davis AK, Barrett FS, May DG, et al. Effects of Psilocybin-Assisted Therapy on Major Depressive Disorder: A Randomized Clinical Trial. JAMA Psychiatry. 2021;78(5):481-489. doi:10.1001/jamapsychiatry.2020.3285. Corrected February 10, 2021. https://doi.org/10.1001/jamapsychiatry.2020.3285
[S21] Carhart-Harris R, Giribaldi B, Watts R, et al. Trial of Psilocybin versus Escitalopram for Depression. New England Journal of Medicine. 2021;384(15):1402-1411. doi:10.1056/NEJMoa2032994. https://doi.org/10.1056/NEJMoa2032994
[S22] Oregon Revised Statutes, Chapter 475A - Psilocybin Regulation (2025 Edition), as supplemented by Oregon Laws 2026 Chapter 109 (HB 4040) and Chapter 123 (HB 4153). Accessed September 2, 2026. https://www.oregonlegislature.gov/bills_laws/ors/ors475a.html
[S23] Oregon Secretary of State / Oregon Health Authority. Oregon Administrative Rules, Chapter 333, Division 333 - Psilocybin (OAR 333-333-1010 through 333-333-8250). Current operative rules. Accessed September 2, 2026. https://www.oregon.gov/oha/PH/PREVENTIONWELLNESS/Pages/Psilocybin-Administrative-Rules.aspx
[S24] Oregon Health Authority, Oregon Psilocybin Services. Information for Licensed Facilitators. Official current implementation guidance page, captured August 25, 2026. Accessed September 2, 2026. https://www.oregon.gov/oha/ph/preventionwellness/pages/psilocybin-information-for-licensed-facilitators.aspx
[S25] Oregon Health Authority, Oregon Psilocybin Services. Information for Licensed Service Centers. Official current implementation guidance page, captured August 25, 2026. Accessed September 2, 2026. https://www.oregon.gov/oha/ph/preventionwellness/pages/psilocybin-information-for-service-centers.aspx
[S26] Colorado Department of Regulatory Agencies, Office of Natural Medicine Licensure. Natural Medicine Licensure Rules and Regulations, 4 CCR 755-1. Current official rule text. Accessed September 2, 2026. https://www.sos.state.co.us/CCR/GenerateRulePdf.do?fileName=4+CCR+755-1&ruleVersionId=11832
[S27] Colorado General Assembly. SB23-290 - Natural Medicine Regulation and Legalization. Chapter 249, Session Laws of Colorado 2023. Accessed September 2, 2026. https://leg.colorado.gov/bills/sb23-290
[S28] Colorado General Assembly. SB24-198 - Regulated Natural Medicine Implementation. Enacted 2024. Accessed September 2, 2026. https://leg.colorado.gov/bills/sb24-198
[S29] Colorado Department of Revenue, Natural Medicine Division. Colorado Regulated Natural Medicine Rules, 1 CCR 213-1. Current operative rules. Accessed September 2, 2026. https://www.coloradosos.gov/CCR/GenerateRulePdf.do?fileName=1+CCR+213-1&ruleVersionId=11721
[S30] Colorado General Assembly. HB26-1325 - Natural Medicine. Chapter 372, Session Laws of Colorado 2026. Accessed September 2, 2026. https://leg.colorado.gov/bills/hb26-1325
[S31] Guo H, Tang L, He M, Tang W, Liu J, Wu S, Yuan S, Wang J, Tang X. Comparative safety and tolerability of ketamine and esketamine for major depressive disorder: a systematic review and meta-analysis. Frontiers in Pharmacology. 2025;16:1681060. https://doi.org/10.3389/fphar.2025.1681060
[S32] Hinkle JT, Graziosi M, Nayak SM, Yaden DB. Adverse Events in Studies of Classic Psychedelics: A Systematic Review and Meta-Analysis. JAMA Psychiatry. 2024;81(12):1225-1235. https://doi.org/10.1001/jamapsychiatry.2024.2546
[S33] Yerubandi A, Thomas JE, Bhuiyan MAN, et al. Acute Adverse Effects of Therapeutic Doses of Psilocybin: A Systematic Review and Meta-Analysis. JAMA Network Open. 2024;7(4):e245960. https://doi.org/10.1001/jamanetworkopen.2024.5960
[S34] Breeksema JJ, Kuin BW, Kamphuis J, van den Brink W, Vermetten E, Schoevers RA. Adverse events in clinical treatments with serotonergic psychedelics and MDMA. Journal of Psychopharmacology. 2022;36(10):1100-1117. https://doi.org/10.1177/02698811221116926
[S35] Halman A, Kong G, Sarris J, Perkins D. Drug-drug interactions involving classic psychedelics: A systematic review. Journal of Psychopharmacology. 2024;38(1):3-18. https://doi.org/10.1177/02698811231211219
[S36] Sarparast A, Thomas K, Malcolm B, Stauffer CS. Drug-Drug Interactions Between Psychiatric Medications and MDMA or Psilocybin: A Systematic Review. Psychopharmacology (Berl). 2022;239(6):1945-1976. https://doi.org/10.1007/s00213-022-06083-y
[S37] Cavarra M, Falzone A, Ramaekers JG, Kuypers KPC, Mento C. Psychedelic-Assisted Psychotherapy - A Systematic Review of Associated Psychological Interventions. Frontiers in Psychology. 2022;13:887255. https://doi.org/10.3389/fpsyg.2022.887255
[S38] Thal SB, Baker P, Marinis J, et al. Therapeutic Frameworks in Integration Sessions in Substance-Assisted Psychotherapy: A Systematised Review. Clinical Psychology & Psychotherapy. 2024;31(1):e2945. https://doi.org/10.1002/cpp.2945
[S39] Phelps J. Developing Guidelines and Competencies for the Training of Psychedelic Therapists. Journal of Humanistic Psychology. 2017;57(5):450-487. https://doi.org/10.1177/0022167817711304
[S40] McGuire AL, Cohen IG, Sisti D, et al. Developing an Ethics and Policy Framework for Psychedelic Clinical Care: A Consensus Statement. JAMA Network Open. 2024;7(6):e2414650. https://doi.org/10.1001/jamanetworkopen.2024.14650
[S41] McHerron D, Barber M, Ham R, Liknaitzky P, Carter A, Gardner J. The Ethical Use of Therapeutic Touch in Psychedelic-Assisted Therapy: A Qualitative Study of Researcher Perspectives and Experiences. Therapeutic Advances in Psychopharmacology. 2025;15:20451253251377191. https://doi.org/10.1177/20451253251377191
[S42] Kruger DJ, Aday JS, Fields CW, Kolbman N, Glynos N, Barron J, Herberholz M, Boehnke KF. Psychedelic Therapist Sexual Misconduct and Other Adverse Experiences Among a Sample of Naturalistic Psychedelic Users. Psychedelic Medicine. 2025;3(1):41-47. https://doi.org/10.1089/psymed.2024.0011
[S43] Hughes ME, Garcia-Romeu A. Ethnoracial Inclusion in Clinical Trials of Psychedelics: A Systematic Review. EClinicalMedicine. 2024;74:102711. https://doi.org/10.1016/j.eclinm.2024.102711
[S44] Grossman DH, Madden KR, Mehtani NJ, Anderson BT, Davis LL, Mitchell JM, Hendricks PS. A systematic review of income and education reporting in psychedelic clinical trials. Nature Mental Health. 2025;3(5):567-574. https://doi.org/10.1038/s44220-025-00417-3
[S45] U.S. Drug Enforcement Administration. The Controlled Substances Act. Accessed September 2, 2026. https://www.dea.gov/drug-information/csa
[S46] 21 CFR 1308.11(d)(29)-(30). Schedule I - Psilocybin and Psilocyn. Accessed September 2, 2026. https://www.ecfr.gov/current/title-21/chapter-II/part-1308/section-1308.11
[S47] 21 CFR 1308.11(d)(21). Schedule I - Ibogaine. Accessed September 2, 2026. https://www.ecfr.gov/current/title-21/chapter-II/part-1308/section-1308.11
[S48] Cherian KN, Keynan JN, Anker L, et al. Magnesium-ibogaine therapy in veterans with traumatic brain injuries. Nature Medicine. 2024;30:373-381. https://doi.org/10.1038/s41591-023-02705-w
[S49] Brunt TM. Rare but relevant: Ibogaine and cardiovascular complications - prolonged QT interval and ventricular arrhythmias. Addiction. 2026;121(6):1616-1621. https://doi.org/10.1111/add.70319
[S50] Rubi L, Eckert D, Boehm S, Hilber K, Koenig X. Anti-addiction Drug Ibogaine Prolongs the Action Potential in Human Induced Pluripotent Stem Cell-Derived Cardiomyocytes. Cardiovascular Toxicology. 2017;17(2):215-218. doi:10.1007/s12012-016-9366-y. https://doi.org/10.1007/s12012-016-9366-y
[S51] Henstra M, Wong L, Chahbouni A, Swart N, Allaart C, Sombogaard F. Toxicokinetics of ibogaine and noribogaine in a patient with prolonged multiple cardiac arrhythmias after ingestion of internet purchased ibogaine. Clinical Toxicology. 2017;55(6):600-602. https://doi.org/10.1080/15563650.2017.1287372
[S52] Oregon Health Authority, Oregon Psilocybin Services. Oregon Psilocybin Services - Administrative Rules and Rulemaking Process. 2026 Annual Rulemaking; revised proposed rules published for public comment September 1, 2026. Accessed September 2, 2026. https://www.oregon.gov/oha/PH/PREVENTIONWELLNESS/Pages/Psilocybin-Administrative-Rules.aspx